
Deadline Nears for Federal Ban on Hemp THC Products   

By Pat Anson

People who suffer from chronic or acute pain in the U.S. are about to lose access to another pain reliever: hemp-derived THC.

On December 11, federal rules are scheduled to take effect that would outlaw any hemp-based product with over 0.4 milligrams of total THC per container. Without a last-minute intervention by Congress, hemp products that exceed that limit will become illegal Schedule One controlled substances.

Hemp is a strain of marijuana that was legalized federally under the 2018 Farm Bill, in part because hemp contains only trace amounts of tetrahydrocannabinol (THC), the psychoactive ingredient in marijuana. 

The thought was that such low amounts of THC could not get people high, and hemp could then be used to make commercial and industrial products, such as textiles and construction materials 

It didn’t take long, however, before companies found ways to concentrate the hemp THC into formulations such as delta-8 and delta-10, which then became widely available in candy, gummies, cookies, tinctures and beverages. 

People who never considered smoking a joint started using hemp-based products for pain relief, such as Jennifer Pace, a Florida woman with Stage 4 cancer.

“Before my diagnosis with breast cancer, I didn’t understand the difference between getting high and using hemp products for pain management. Neither did my family,” Pace wrote in an op/ed in The Well News. “But living with cancer completely changed our perspective, as I witnessed firsthand how these products could help me manage my symptoms and maintain my quality of life.

“Hemp-derived edibles quickly became part of my approach to pain management. They not only provide quick relief but, unlike opioids, allow me to remain more alert and engaged in my daily life.”

Pace is now worried about losing access to those edibles, as are thousands of other Americans, including military veterans.

“Veterans have sacrificed for our country, and they deserve safe, responsible options for managing chronic pain, PTSD, anxiety, sleep problems, and other health conditions. Many veterans, working with their healthcare providers, rely on hemp products as an alternative to opioids,” the Veterans of Foreign Wars (VFW) and other veterans groups wrote in a letter to House and Senate leaders. 

“If Congress fails to act, the products they depend on will suddenly become illegal, forcing them to turn to an unregulated market or go without. Our veterans deserve better.” 

Rather than ban hemp products completely, the veterans groups want Congress to enact age purchasing limits, require accurate labeling, and eliminate the use of “child friendly” packaging on hemp-derived products like cookies and snacks.

It’s unclear if a lame duck Congress has the political will to make those changes. There is opposition from some Republican senators – who still have a majority in the Senate.

“Congress closed the hemp loophole more than a year ago to end an industry that never should have existed,” Sen. Ted Budd (R-NC) said in a social media post. “I will not support any year-end package that extends, delays, or builds a regulatory framework around products that fuel addiction, endanger our children, and weaken our workforce.”

If hemp THC is outlawed, it creates a curious situation. Medical marijuana products approved at the state level were moved to Schedule III earlier this year by the DEA, which allows for medical use. That option is available to hemp consumers in most states, but not in states that have yet to legalize medical marijuana.

"Our main concern is that people who use hemp THC products for chronic pain are about to lose legal access on three weeks' notice, with no transition period and, in much of the country, no legal alternative,” said Andrew Damian, co-founder of Dr. Weedy, a telehealth service that provides medical marijuana evaluations.

“A state medical program isn't open to everyone. Eight states have none: Idaho, Indiana, Kansas, North Carolina, South Carolina, Tennessee, Wisconsin and Wyoming. Texas allows only low-THC products, and Nebraska has no working card registry yet. Pain patients there get no legal replacement.”

Legislation to extend the hemp deadline may be inserted into a stopgap spending bill that coincidentally needs to be passed by December 11. Given how contentious spending bills can be — that further muddies the water.

In the meantime, people in pain like Jennifer Pace are asking for help.

“If Congress is serious about improving our health care system, it must consider how patients can access the tools and resources they need to live with and fight their diseases,” she wrote.

“For many of us, treatment is not just about how long we live. It is also about how well we can live. Ensuring patients have options to manage their symptoms and maintain their quality of life should be part of that conversation.”
How To Survive Thanksgiving With Chronic Pain

By Crystal Lindell

Unfortunately, you can’t just flip a switch and turn off your chronic pain just because it happens to be Thanksgiving. Even celebrations have to be navigated differently when your body hates you.

I’ve been dealing with chronic pain since 2013, which means I’ve survived my fair share of family gatherings while living with pain. Below are some realistic tips for getting through the day of thanks, and all the holidays that follow.

Plan for Rest Days Before and After Gatherings

My fiance Chris and I are doing one Thanksgiving on the official Thursday holiday, and the other side of the family on Saturday. So I have a full day in between to recover from the first one.

I know that my body is going to be shot after all that cooking and socializing, and I also know that it takes me longer to recover from such events than it did pre-chronic pain.

I can’t just go home, get a good night's rest, and then do it all again tomorrow. I need about 15 hours of sleep first.

So, instead of pushing myself to do what I “should” do during over holidays – and jam packing my schedule to see as many people as possible -- I’m just going to accept that I need to rest. I won’t feel guilty for sleeping through that entire Friday to recharge my body. 

I highly recommend you do the same.

Embrace Pre-Made and Take Out Meals

One of the best ways to get through a major holiday is to outsource as much of the labor as possible.

If you have to cook, or God forbid host, don’t be afraid to have someone else make the food – even if that someone else is the restaurant down the street.

Lots of grocery stores also have great pre-made food options either in the deli or even the frozen food section.

Depending on your pain levels, maybe that means buying an entire Thanksgiving meal that’s pre-made. Or maybe it means just getting a few items like desserts. 

Just because something isn’t homemade, doesn’t mean it’s not served with love. Do what you’ve got to do to get food on the table, so you can focus on what really matters – arguing politics with your extended family while rooting against each other’s football teams.

Consider a Daytime Nap 

This one may sound obvious to all the grandpas out there – who are known for their after-Turkey nap. But if you’re not a grandpa, you may feel like it’s weird to sneak away to get some sleep right after dinner.

I’m here to tell you, not only is it not weird, it’s actually amazing. The right nap can mean you get twice as many socializing hours in with your family before you have to call it a day.  

So just find a couch or a guest room and get some rest.

Try to Ration Pain Meds

I know this one is going to be controversial, but we’re talking about real life here, so I’m going to give real life advice.

While I fully understand that many people aren’t able to get opioid pain medication anymore, if you do have any type of pain relievers, I have found it helpful to have a few extra available for big events.

Yes, that likely means taking a little less on a different day, but a good way to do that is to skip a dose on “good” pain days so that you have extra ones on your more difficult days.

Most doctors do not want patients doing that with their pain medication, but I’m not a doctor. I’m a pain patient who learned long ago that having an extra Norco available can really make or break a holiday gathering.

Your Presence Is All Your Loved Ones Care About

Maybe you didn’t have the energy to go full glam. Or maybe the only way you can show up to dinner is in pajamas.

It’s all good.

Thanksgiving is really just about spending time with those you love, however they may be dressed.

And it’s about finding even small things to be thankful for, in spite of all the things that make life hard. 

Sure our bodies are breaking down and making life miserable, but at least we get the simple pleasure of eating French silk pie for dessert and Thanksgiving leftovers all weekend.

‘All Kratom Is Unsafe’: Senators Want DEA to Reconsider Scheduling 

By Pat Anson

Eight U.S. Senators are making a last-minute plea to the Trump Administration to scrap plans to classify 7-OH (7-hydroxymitragynine) and other concentrated kratom alkaloids as illegal Schedule One controlled substances. 

In a letter to the heads of the DEA and FDA, Senate Judiciary Committee Chairman Chuck Grassley (R-Iowa) and seven of his Republican colleagues claim that “all Kratom is unsafe” and called on the agencies to reconsider their October scheduling order – which could take effect any day.

That order will essentially ban most forms of 7-OH and synthetic kratom derived products – while keeping natural leaf kratom legal. Grassley and his colleagues say that would be a mistake.

“Kratom is an opioid. Interested parties’ word play often involves differentiating between ‘natural’ and ‘synthetic’ products. Surely artificially enhanced Kratom products are often more dangerous, but that does not mean that so-called ‘natural’ ones are safe. Nor does marketing a product as ‘natural’ make it a dietary supplement or recognized as safe,” the letter states.

“The psychoactive alkaloids of the kratom plant are potentially dangerous substances that should be treated with caution, particularly given the lack of adequate regulation on its products.”

In a previous letter, Grassley and two other senators called on the Trump Administration to “consider scheduling the entire kratom plant.” The new letter doesn’t go that far, but shows that Grassley’s views on kratom are gaining some traction — and signatures — in Congress.

Sens. Susan Collins, Rick Scott, Mike Crapo, Bill Cassidy, Jerry Moran, Shelley Moore Capito and James Risch co-signed the new letter.

The DEA’s October scheduling order is a revised version of a previous order that would have banned 7-OH and all other synthetic forms of kratom. The new order is a bit more lenient, allowing for trace amounts of 7-OH and the alkaloid mitragynine pseudoindoxyl (MP) in tablets, gummies and liquid shots, provided they are limited to 1 mg per serving. That’s twice the amount of 7-OH allowed in the earlier order, but is well below what is currently on the market.   

Grassley and his colleagues say the new scheduling order is too lenient and would allow addictive products on the market.

“Kratom is a drug in any form with addictive properties, and we believe this combined threshold level for 7-OH and MP set by DEA is inappropriately high and unsound. MP is a semi-synthetic opioid that is more potent than morphine. To date whether MP is naturally occurring in the plant is unclear. If the Administration’s goal is to remove all unsafe products from the shelves, particularly synthetic or enhanced kratom products, this order misses the mark,” the letter states.

The senators want the FDA to explain why it supports the new scheduling order and for the DEA to revert back to its original one. They asked for a reply by November 30.

The DEA’s amended order is largely in response to a lawsuit by the American Kratom Association (AKA), which represents natural leaf kratom vendors who are losing market share to 7-OH and other synthetic manufacturers.

The AKA supported the scheduling of 7-OH, but wanted a “carve out” for mitragynine pseudoindoxyl, which the DEA banned just three months ago. The AKA dismissed its lawsuit once the DEA agreed to the carve out. .

At this late date, it’s unclear if the senators’ letter could lead to a delay or further changes in the DEA’s scheduling order.  

Kratom leaves have been used for centuries in Southeast Asia as a natural stimulant and pain reliever. Their active ingredients – 7-OH and dozens of alkaloids – occur naturally in kratom in trace amounts. But in recent years manufacturers have found ways to concentrate the alkaloids in new products – essentially turning a mild pain reliever into a potent product with opioid-like effects. 

Federal efforts to schedule kratom under the Controlled Substances Act have been fraught with problems and poor science for over a decade. 

In 2016, the DEA tried to schedule kratom as an illegal drug, but withdrew the proposal after a public outcry. A top federal health official later admitted the scheduling request was based on “embarrassingly poor evidence & data” from the FDA and could result in a “substantial risk to public health” if kratom leaf were made illegal.

A public policy think tank recently warned that banning leaf kratom, 7-OH, and other kratom-derived synthetics could have unintended and harmful consequences. Consumers who are dependent on those products could go into withdrawal or turn to illicit drugs on the black market.  

Overdoses Dropped When Prescribing Fell for Pregabalin

By Pat Anson

Prescription opioids get most of the attention, but there’s another class of medication that is often associated with misuse, dependence and overdose: gabapentinoids. 

Originally developed to treat epileptic seizures, gabapentinoids like pregabalin (Lyrica) and gabapentin (Neurontin) are often prescribed off-label as an alternative to opioids, even though there is little evidence to support their use as analgesics. Sales of Lyrica and Neurontin tripled over a decade ago, just as prescriptions for opioids became harder to get in the U.S. and other countries.

That overprescribing led to problems around the world. In the UK, about a third of drug deaths in 2022 involved a gabapentinoid; while in Australia, overdoses involving pregabalin increased by 54% between 2005 and 2016. 

Gabapentinoids alone rarely cause death. But when taken along with opioids, benzodiazepines, anti-depressants or muscle relaxants, gabapentinoids heighten the risk of abuse and overdose.

A new study in Australia shows what can happen when pregabalin prescribing is reduced, and doctors and patients are better educated about the drug’s potential risks. Overdoses in Australia involving pregabalin have fallen 47% since stricter scheduling was adopted and boxed warnings were added to prescription labels.  

“After many years of escalating pregabalin use and overdose in Australia, rates appear to have plateaued and started to decline since 2018,” wrote lead author Rose Cairns, PhD, an Associate Professor in the School of Pharmacy at University of Sydney, in The BMJ.  

“While our findings are positive, pregabalin use and overdose remain high, with dispensing rates still far outstripping what would be expected if pregabalin was prescribed for approved indications alone. Therefore, ongoing monitoring is needed and we should consider further interventions, including additional scheduling restrictions.”

Cairns and her colleagues say caution is warranted because almost half of Australians taking pregabalin also use opioids. About 13% of patients prescribed pregabalin are considered at high risk of abuse. 

Pregabalin is FDA-approved to treat diabetic nerve pain, fibromyalgia, nerve pain from shingles and spinal cord injuries; while gabapentin is approved to treat epilepsy and shingles pain. Both drugs are also widely prescribed off label to treat back pain, depression, migraine and post-operative pain. Studies have estimated that gabapentin is prescribed off-label up to 95% of the time.  

"Despite this relatively narrow range of approved indications, gabapentinoids are considered 'blockbuster' drugs," wrote Cairns. "High-income countries have the highest rates of gabapentinoid consumption, while low- and middle-income countries have had the highest consumption growth in recent years. Most of this consumption is driven by off-label use for non-registered indications." 

Patients have long complained that gabapentinoids are ineffective for pain, and have side effects like brain fog, dizziness, weight gain and mood disorders. Recent research has also linked gabapentin to dementia.

A recent study of Medicaid patients found that being prescribed gabapentinoids for acute low back pain increases the risk of overdosing or developing opioid use disorder nearly as much as taking opioids. Despite the documented risks of taking them together, nearly 60% of U.S. patients on long-term opioid therapy are also prescribed gabapentinoids.

DEA Plans Minor Cuts in Opioid Supply in 2027

By Pat Anson

The U.S. Drug Enforcement Administration is proposing only minor cuts in the supply of oxycodone, hydrocodone, and other Schedule II prescription opioids in 2027. 

If the DEA’s plans are finalized after a 30-day public comment period, it will be the 11th consecutive year the opioid supply has been reduced in the United States – although the cuts are not nearly as steep as they were in prior years. 

Since 2015, DEA has reduced the supply of most opioids by about 70 percent.  

The DEA announced its plans for 2027 in the Federal Register. Under the Controlled Substances Act, the agency has broad legal authority to set annual aggregate production quotas (APQs) for drug makers – in effect telling them the amount of Schedule I and Schedule II chemicals and medications they can produce. 

In setting its quotas, the DEA relies on the Food and Drug Administration to provide estimates of the medical need for opioids and other controlled substances. In July, the FDA told the DEA there would be a nearly 10% decline in demand for Schedule II opioids in 2027.

“FDA predicts that levels of medical usage for schedule II opioids in the United States in calendar year 2027 will decline on average 9.68 percent from calendar year 2026 levels. These declines are expected to occur across a variety of schedule II opioids including fentanyl, hydrocodone, hydromorphone, oxycodone, and oxymorphone,” the DEA said.   

It’s important to note that medical usage is different from “medical need.” Doctors aren’t prescribing as many opioids as they used to, so while the need for pain relief hasn’t changed and may have even increased, the number of prescriptions being written for opioids has fallen – which is driving the decline in “medical usage.” 

In any case, the DEA’s proposed quotas for 2027 are largely unchanged from this year, with only a few minor reductions of less than one percent:

Schedule II Opioid Production Quotas for 2027

  • Oxycodone        0.81% Decrease

  • Hydrocodone      0.50% Decrease

  • Fentanyl              0.03% Decrease

  • Oxymorphone     0.02% Decrease

  • Codeine              Unchanged

  • Morphine             Unchanged

  • Hydromorphone  20.8% Increase

The DEA says the 20% increase in the allowed amount of hydromorphone came after a request from drug manufacturers to raise the quota due to growing domestic shortages of hydromorphone hydrochloride injectables, which are primarily used in hospitals for surgery and severe trauma. 

A 142% increase in exports of hydromorphone contributed to those shortages, which the DEA recently addressed by allowing manufacturers to produce more hydromorphone in the final months 2026. The increase in the hydromorphone quota is being carried forward into 2027.

The DEA is also raising the 2027 production quotas for stimulants used to treat patients with attention deficit hyperactivity disorder (ADHD). The FDA was concerned about shortages of those drugs due to the growth of ADHD diagnoses via telemedicine, as well as supply chain problems and manufacturing issues.  

Public comments on the DEA’s proposed 2027 quotas will be accepted until December 10, 2026. To leave a comment, click here.

The APQs will be released a few weeks later – perhaps not until early 2027. If that is the case, it will be yet another violation of the Controlled Substances Act by the DEA, which requires the agency to publish its final quotas by December 1. 

The December deadline is important because it gives the pharmaceutical industry time to prepare for the coming year by adjusting their drug manufacturing and distribution schedules – a process that can take as long as six months.

Last year, the final quotas were not published until January 5. The DEA’s repeated failure to meet the December 1 deadline has contributed to drug shortages like the current ones for hydromorphone and other injectable analgesics 

It’s Rare for Cancer Patients to Overdose on Opioids

By Crystal Lindell

Although most medical guidelines exempt cancer patients from restrictions on the use of opioids, it’s not uncommon for a cancer patient to be denied opioid pain medication by a doctor or pharmacist.

Some providers take the guidelines so seriously they won’t prescribe or fill an opioid prescription – even for someone dying of cancer — fearing it could lead to abuse, addiction, or even an overdose.

A large new study published in JAMA shows how ridiculous that practice is. Out of 554,316 Canadian adults being treated for solid cancer tumors, only 191 of them had a fatal opioid overdose. That’s 0.03%.

Non-fatal opioid overdoses were a bit more common, with 1,591 of cancer patients in the study surviving an overdose. That one comes out to 0.3%.

The overdose rate was higher for patients with advanced cancer or on high opioid doses, but the overall rate is still low – well below 1%. 

Unfortunately, researchers concluded that access to opioids should be limited for the other 99% of cancer patients. If opioids are prescribed, they recommend that naloxone should be co-prescribed to reduce the “rare” risk of an overdose even further.

“Opioids are essential for cancer pain management but carry risks, with opioid overdoses being the most severe,” wrote lead author Jenny Lau, MD, a Palliative Care Physician at the Princess Margaret Cancer Centre in Toronto. “(Our) findings suggest that opioids should be prescribed at the lowest effective dose for symptom management, with close monitoring and routine assessment for opioid overdose risk.” 

This conclusion was made despite the fact that the overdose rate for cancer patients is actually much lower than the general population.

This was noted by the researchers themselves. In Canada, the fatal overdose rate in the general population is estimated at 19 for every 100,000 people. The U.S. overdose rate is slightly higher. 

By comparison, the overdose rate in the cancer study was only 6.5 per 100,000 – about 66% lower than the general population.

“Consistent with past oncology studies, we found that the incidence of opioid overdoses was relatively low among patients with cancer,” wrote Lau. 

Perhaps this is a bit of a stretch, but doesn’t that suggest that giving cancer patients opioid medication lowers their risk of overdose? Or that having cancer reduces your risk of an overdose? That’s absurd of course, but that’s what the data implies.

While any overdose is a tragedy, it’s possible that other factors are at play for the cancer patients, such as having other health problems, weakened immune systems, and taking multiple medications.

It’s also unclear how many of the 554,316 patients even had an opioid prescription because the study never lays that out. The researchers did note that those who received an opioid prescription in the prior 30 days were 71% more likely to experience an overdose. 

The overdose risk increased by 2-fold if patients received doses higher than 50mg morphine milligram equivalents (MME) per day. The overdose risk was also higher for younger patients, those with gynecologic cancers, and patients with a diagnosis of opioid use disorder.

Patients who overdosed were more likely to have higher pain scores and higher distress scores. Perhaps that was because they took more medication in hopes of alleviating their pain.

The urge to study patient populations like this is understandable, especially in regards to overdoses. That said, it seems a bit of a reach to take mixed results like this and make a sweeping conclusion that doctors should be limiting opioid prescriptions to cancer patients.

In fact, I’d argue the opposite is true. The rates of overdose were so low that they show just how rare an overdose actually is, and how safe prescription opioids can be when used by people who really need them.

RFK Jr. Thinks He Saved Thousands of Lives. But It May Have Been 7-OH.

By Crystal Lindell

Health and Human Services Secretary Robert F. Kennedy Jr. recently claimed during a press conference that the Trump administration has saved tens of thousands of American lives.  

He said opioid overdoses were down by 30% and the number of opioid prescriptions were cut in half, yet the news media was ignoring it.

“We have saved 20,000 lives,” RFK Jr. said. “What we’re doing in our various programs is working, and it’s working for the American public. It’s another fantastic accomplishment by the Trump administration that everybody said could not happen. But it’s getting done and nobody’s covering it.” 

As someone who’s on the ground in the rural Midwest, where overdose deaths have ravaged the region, I’m here to report the truth: In my observations, RFK Jr. hasn’t saved any lives, but legal 7-hydromitragynine (7-OH) has. 

I can’t prove it scientifically, but I can tell you what I have witnessed. Former fentanyl users suddenly thrived when they started taking the concentrated kratom alkaloid.  

Of course, the most depressing part about all of this is that it’s RFK Jr. who’s leading the push to make 7-OH illegal. He has played a major role in getting the DEA to make 7-OH an illegal Schedule One drug, which could happen any day now.

When the plan was first announced, Kennedy said: “We’re taking action on 7-OH as a critical step in the fight against opioid addiction. We will protect the health of our nation’s youth as we advance our mission to Make America Healthy Again.”

But it’s 7-OH that has been doing a lot of the heavy lifting in fighting opioid addiction. Many long-time opioid addicts have turned to it to stabilize their lives. 

Overdose deaths actually started declining in 2023, two years before President Trump’s second term began, and opioid prescriptions began falling a decade ago during the Obama administration. And yes, we covered it.

7-OH Saves Lives

Coincidentally, 2023 is the same year that 7-OH products first became widely available.   

“There's probably roughly 75,000 people walking the earth today that wouldn't be here, and hundreds of thousands of others that have used 7-OH to completely stop taking a street drug,” American Shaman founder and 7-OH producer Vince Sanders told PNN nearly a year ago.

I fully expect overdose deaths to start creeping back up when the 7-OH ban goes into effect. To put it bluntly: people are going to die because of RFK Jr.’s actions.

The need for effective pain relief won’t just go away, but will shift into more dangerous territory, like street fentanyl, as a public policy think tank recently warned.   

Here’s the real truth about 7-OH from someone who uses it to treat debilitating chronic pain: It has been a godsend. Aside from the fact that it’s actually effective at treating pain, it’s also a partial agonist at the mu-opioid receptor, which gives it a ceiling effect that helps people naturally limit their dose. 

Best of all, unlike actual opioids, 7-OH does not cause respiratory depression – which means people don’t die when they take it. That’s why we haven’t seen a bunch of overdoses blamed solely on 7-OH. After all, if 7-OH was actually causing deaths, we’d see bodies in the streets given how accessible it is. Or was, depending on where you live.   

Plus, because it has remained legal in most states, 7-OH has helped people who used to rely on street drugs stabilize their lives. I have seen it first-hand among loved ones who have been more stable and healthy than they have been in years. 

No more spending all day trying to get in touch with a shady drug dealer who could be selling you crushed Benadryl. They could simply go to a smoke shop, buy a trusted 7-OH brand, and expect about the same level of effectiveness as the last time they purchased it.

My fiancé went to high school here in the rural Midwest, and has lost countless friends to overdoses. So many have died, that it’s hard to remember the full list of their names.

But something magical happened over the last couple years. People stopped dying of ODs. The last one we heard about was in July 2024.  

Now that we are in the final days of legal 7-OH, I’m seeing a big push in the news media and by addiction treatment providers urging people to use Suboxone to get off 7-OH. That’s like pushing people to use cocaine to get off coffee. It’s absurd and dangerous, and will just lead to users developing a significantly worse opioid addiction.

There’s a lot of advocacy around 7-OH where users plead with the general public to get them to understand just how helpful it’s been to chronic pain patients, people with opioid addiction, and military veterans.

I think there’s a major flaw in that approach though. The problem is that many people don’t care about those groups. They think people should just suck it up if they have chronic pain, and they take sick pleasure in seeing opioid addicts suffer through withdrawal. . 

But there’s a saying about disability, and by extension chronic pain: “It’s the only minority group you can join at any time.” You never know when you could get in a car accident, or fall in love with a veteran, or watch your child develop opioid addiction.

And when those things happen, you will be desperate to find the safe and effective relief that 7-OH offers. But it will likely be too late, because the Trump administration will have already made it a Schedule One drug.

I want to end this column with some practical advice for any 7-OH users who may be forced to stop using it over the next week: TAPER! 

I am not a doctor but I have tapered off 7-OH myself. If you taper down slowly, taking a little less every day, for many users the withdrawal symptoms are almost zero. When you get to a very low dose, start working in coffee and kratom powder to ease the transition even more. 

Losing legal 7-OH is going to be devastating for a lot of people, and it’s going to lead to more overdoses. And when that happens, RFK Jr. – a former heroin user himself – won’t be attending any of the funerals, offering condolences, or taking credit for the needless deaths. 

Kratom Bans Come With Risks

By Pat Anson

As federal, state and local governments move to restrict or ban sales of kratom products, a public policy think tank is warning that excessive regulation could have unintended and harmful consequences.  

Kratom comes from the leaves of a tree that grows in Southeast Asia, where it has been used for centuries as a natural stimulant and pain reliever. In recent years, millions of Americans have started using kratom products to relieve pain, anxiety, depression and withdrawal symptoms. 

“Regulating the availability of kratom does not eliminate the health needs of people who use it,” warns Heather Trela, Director of Operations and a Fellow at the Rockefeller Institute of Government. 

“How to aid kratom users, especially those who may not have realized that they have developed dependency on it, should be a consideration of any local government thinking about banning or regulating the substance in ways that don’t themselves result in potential harm.”

In its natural state, leaf kratom has mild opioid-like qualities. But concentrated forms of 7-hydromitragynine (7-OH) and other kratom alkaloids are more potent and have the potential to cause dependency and addiction. They do not cause respiratory depression the same way opioids do, but dozens of overdose deaths – most involving other drugs – have been blamed on kratom products..   

Prompted by sensational stories calling 7-OH “gas station heroin,” dozens of states and local governments have prohibited sales of 7-OH and other semi-synthetic kratom products. The Trump Administration is soon expected to join them by having the DEA classify 7-OH and other concentrated kratom products as illegal Schedule One controlled substances. Natural leaf kratom would not be scheduled.

In a blog on the Rockefeller Institute’s website, Trela says the federal and state bans could force kratom consumers into withdrawal or to use more dangerous illicit substances. 

“For individuals who have developed dependence, abruptly losing access to the substance may lead to withdrawal symptoms and a need for clinical support. Tennessee’s 2026 ban has already resulted in an increase in people seeking treatment for withdrawal, and similar patterns have been observed in Florida and Kansas,” wrote Trela.

“Withdrawal symptoms can include joint pain, insomnia, feverish sensation, tremors, itching over the body, and chills, and those who are going through withdrawal may turn to other drugs, like fentanyl, to alleviate the symptoms. A sudden influx of patients experiencing kratom detox can be a challenge for local healthcare resources and can increase the potential of an illicit market for kratom and other drugs.” 

As PNN has reported, addiction treatment centers are seeing an influx of patients seeking help for kratom withdrawal, but there is little evidence they are being overwhelmed with new patients. 

Millennium Health, a drug testing company that works with addiction treatment centers nationwide, says less than 4% of its urine drug screens tested positive for kratom alkaloids in June. By contrast, 13% of Millennium’s urine screens tested positive for fentanyl and 11% tested positive for stimulants. 

Black Market Kratom

As often happens when a drug is banned or sales are restricted, it starts showing up on the black market. Kratom is no exception. Even in states where kratom and its semi-synthetic derivatives are banned, they are sold “under the counter” by smoke shops, gas stations and online vendors. 

Such is the case for the recent deaths of two college students at the University of Mississippi, who were illegally sold 7-OH tablets at a smoke shop. A 2025 Mississippi state law limits kratom sales to customers over age 21 and bans all synthetic forms of kratom. Both students were under the age limit.

In California, kratom sales are prohibited at brick-and-mortar stores, and state regulators recently bragged about seizing or destroying $10 million worth of kratom and 7-OH products over the past year. Nevertheless, online vendors continue shipping leaf kratom and 7-OH products into the state with little or no interference.

The Rockefeller Institute says passing laws that ban the sale or possession of kratom have little meaning when the laws are not adequately enforced — in effect creating a gray market for them.

“Kratom products may circulate in and out of inventory at gas stations, convenience stores, smoke shops, and wellness stores, and keeping track of who is selling what and where can require a fair amount of effort as well as resources,” wrote Trela. 

“Ultimately, the effectiveness of local kratom regulations will depend not only on what governments seek to prohibit, but also on how they implement and enforce those restrictions and what resources they make available to affected residents.”   

Little Evidence That Workplace Ergonomics Help

By Pat Anson

When computers first started entering the workplace in the 1980’s, there was a surge in complaints about carpal tunnel syndrome and musculoskeletal injuries caused by repetitive and awkward movement.  

That led to strong demand for ergonomic solutions, such as chairs with lumbar support, stand-up desks, split keyboards, and even vertical mice. Ergonomic products and consulting quickly grew into a $56 billion a year industry  

But a new Cochrane review found little evidence that ergonomic interventions relieve pain, reduce sick days, prevent disability, or improve quality of life compared with no treatment.

Led by researchers at the University of Technology Sydney in Australia, the review analyzed 20 clinical trials involving nearly 2,500 people with work-related injuries to the arm, neck or shoulder. Most of the participants used computers in their job, while the rest were factory or slaughterhouse workers. 

Overall, ergonomic interventions were less effective than exercise, though small benefits may occur for certain injuries, such as people with rotator cuff tendinitis.

“Ergonomic interventions can be a big financial burden for organizations,” says lead author Poonam Mehta, PhD, Senior Lecturer at Graduate School of Health (Physiotherapy), University of Technology, Sydney.  “Our findings suggest that, on current evidence, these measures alone shouldn’t be expected to reduce pain or sick leave in the short term. Employers may want to weigh that against the cost.

“We’d need more evidence to confirm this, as there is not much high-quality research in this area.”

That lack of evidence and high quality research is surprising, given the amount of money invested in ergonomics. Researchers say no data is available on the recurrence of injury or complaint, and there is little data on work-related outcomes beyond sick leave after ergonomic interventions.

Ergonomic strategies may still have value as part of workplace safety and training programs, but supporting evidence is limited.

Instead of investing hundreds of dollars in a stand-up desk to reduce back and neck strain, there are cheaper solutions. You can make it easier to see computer screens by increasing the font size or by getting a pair of computer reading glasses.

Losing a Diagnosis Can Be Just as Difficult as Getting One

By Esca van Blarikom

When actor Christina Applegate revealed that she had been misdiagnosed with multiple sclerosis (MS), she described the experience as “very unnerving” and “really confusing”.

For five years, MS had provided an explanation for her symptoms. Now, although those symptoms remained, the diagnosis that had helped her make sense of them was gone.

“I haven’t gotten better… If anything, I’ve gotten worse in some ways,” she explained. She also described feeling that she had lost the “reason” that had helped her make sense of her daily struggles.

Being told you don’t have a disease might seem like good news. But for someone living with symptoms, losing a diagnosis can mean losing an explanation for their suffering, along with the hope that explanation provides.

My ethnographic research into the experiences of people living with multiple conditions helps explain why. Through interviews and observations, I explored how diagnoses shape people’s understanding of their symptoms, their expectations for treatment and their sense of what the future might hold.

One participant in my London-based study had spent years living with debilitating back pain, struggling to get out of bed in the morning. After tests and referrals, a rheumatologist suggested that her symptoms might have an inflammatory cause.

Although this was only a possible diagnosis, it changed how she understood her condition. The specialist introduced medical terms that helped her make sense of symptoms that seemed confusing and unpredictable.

For the first time, there appeared to be an explanation for her suffering. The possibility of identifying an inflammatory condition also offered hope of treatment and specialist care.

But that hope was short-lived. Weeks later, a scan showed no evidence of the suspected inflammation. She was discharged from the clinic without the answers she had hoped for.

Her symptoms had not disappeared, and in the months that followed, her mental health deteriorated markedly.

Unlike Applegate, this participant had never received a confirmed diagnosis that was subsequently withdrawn. But both experiences reveal how much can be invested in a medical explanation, even before it is established.

For the woman in my study, the disappointing test result meant losing a possible way forward after years of uncertainty.

How Diagnoses Shapes Experience

A diagnosis can influence much more than the treatment someone receives. It can also change how they interpret their symptoms and what they expect from their illness.

Research suggests that the attention we pay to bodily sensations can influence how we experience and report them.

In a 2024 experimental study, researchers found that repeatedly asking people about their symptoms increased the number they reported. This effect was particularly pronounced among people with higher levels of health anxiety or existing symptom distress.

These findings do not mean that symptoms are imagined or caused by receiving a diagnosis. They suggest that our awareness and interpretation of bodily sensations can be influenced by the circumstances in which we experience them.

A diagnosis can also create new fears.

When Applegate first received her MS diagnosis, she spoke about experiencing a profound depression and feeling fatalistic about her future.

People with physical health conditions have an increased risk of depression, although this can reflect many factors, including the effects of illness itself.

Another participant in my research described how her quality of life deteriorated after receiving a diagnosis of a chronic condition.

Before the diagnosis, her symptoms had been difficult to interpret. Afterwards, she increasingly understood them as possible signs of deterioration.

She felt that her quality of life had declined significantly following the diagnosis, rather than simply after the onset of her symptoms.

This illustrates how receiving a medical explanation can alter someone’s expectations about their future, particularly when a condition is presented as chronic or difficult to treat.

Research on nocebo effects offers one possible insight into the relationship between expectations and symptoms. Experimental studies have shown that negative expectations can increase experiences of pain through psychological and physiological processes.

This does not establish that the diagnosis caused my participant’s deterioration. However, it helps illustrate why the expectations surrounding illness deserve attention alongside its physical effects.

What Happens When the Diagnosis Disappears

A diagnosis can provide access to treatment, but it may also offer recognition, reassurance and a sense of belonging.

Applegate has spoken about finding support within the MS community. Losing her diagnosis therefore raised questions extending beyond her medical treatment, including her place within a community that had become important to her.

For people with persistent symptoms, the absence of a diagnosis can also create difficulties in having their experiences understood and taken seriously.

Researchers studying unexplained symptoms have highlighted the disadvantages people can face when they lack a shared explanation for what they are experiencing.

This is why a negative test result does not necessarily resolve a patient’s difficulties. It may rule out one possible cause while leaving the symptoms, and the need for care, unchanged.

The challenge for healthcare professionals is to communicate diagnostic uncertainty without leaving patients feeling abandoned.

A 2024 study of GP consultations found that doctors varied considerably in how they explained plans for managing uncertain diagnoses. Some offered detailed guidance, while others provided less information about what patients should do if symptoms persisted or worsened.

For patients who have lost a diagnosis, continuing care might involve explaining why the original diagnosis has changed, acknowledging the distress that this can cause and agreeing on the next steps for investigation or symptom management.

These conversations also need to recognise that ruling out a particular disease does not invalidate the symptoms someone continues to experience.

Applegate’s experience illustrates something important about the role diagnoses play in people’s lives. They can shape how we understand our bodies, our relationships with others and our expectations for the future.

When a diagnosis is withdrawn, those understandings may have to be rebuilt, even as the symptoms that prompted the original investigation continue.

For doctors, the responsibility does not end when a diagnosis is ruled out. Patients still need help making sense of what is happening to them, especially when medicine cannot yet provide a clear answer.

Esca van Blarikom, PhD, is a researcher of medical anthropology for the Department of Global Health & Social Medicine at King's College London.

This article originally appeared in The Conversation and is republished with permission.   

Mayo Clinic Launches AI Chatbot for Doctors

By Crystal Lindell

If you’ve ever shared with a doctor medical information or advice you found online, they may have been annoyed or defensive. After years spent in medical school and/or residency, many doctors dislike anything that questions their expertise – especially if it came from the Internet.

Which makes a new artificial intelligence (AI) program launched by the Mayo Clinic all the more interesting.

Starting this month, the world renowned medical center is launching a new chatbot called the Clinical Decision Support (CDS) solution. The AI-driven chatbot is not for patients, but for the Mayo Clinic’s own doctors and healthcare providers. It will cover more than 35 medical specialties and have access to patient health records, providing “industry-standard medical information” that can “help clinicians reason through complex cases.” 

"Clinicians have access to a vast amount of medical knowledge, but finding relevant information for individualized patient care takes valuable time," says Maneesh Goyal, chief operating officer of Mayo Clinic Platform. 

"With this new solution, we are bringing trusted Mayo Clinic knowledge directly into the clinical workflow so clinicians can spend less time searching for information across multiple resources and more time focused on patient care." 

In other words, Mayo Clinic doctors will be doing the same thing patients do – searching for answers to their health questions.

The Mayo Clinic clarified that its doctors will still be responsible for all medical decisions, regardless of their use of AI. 

"The CDS solution is designed to assist healthcare professionals as they make patient care decisions; it does not replace clinical judgment," said Gelareh Zadeh, MD, chair of the Department of Neurosurgery at Mayo Clinic in Rochester. "Mayo Clinic physicians have provided feedback on the different tools to ensure the solution supports clinicians and reflects Mayo Clinic's approach to patient care." 

A press release says the new chatbot will be evaluated for “safety, effectiveness, privacy, security and clinical value, with appropriate human oversight and ongoing monitoring.”  

As a patient, I’m hopeful that Mayo Clinic would only use an AI chatbot if they felt comfortable with its accuracy and security. But as an AI user, I’m skeptical. 

Interestingly, the Mayo Clinic itself shared an article in April that asked, "Can you trust AI for health advice?" The answer they gave is essentially no, with five reasons cited: 

  1. Diagnosing and treating illness is too complex for a machine

  2. AI can be wrong, even when it sounds confident

  3. AI-created information may be biased

  4. AI spreads misinformation

  5. People and AI don't communicate well together

Mayo Clinic providers would be wise to keep those five cautions in mind as they use their own chatbot. 

PNN has published multiple stories about the risks of using AI in healthcare. One recent article was about a woman who used ChatGBT to seek advice on how to taper off her seizure medication. The advice she received may have led to her death. 

We also published a warning to older adults about how they need to be cautious about taking medical advice from chatbots. 

"Using AI for health information can be particularly fraught because chatbots can be so helpful in explaining complex medical information, but also risky if users automatically trust the responses they receive,” warned Robin Brewer, PhD, an Associate Professor at the University of Michigan.

The hope is that the Mayo Clinic’s chatbot will be more accurate than ChatGPT, but it will take time and usage to reveal if that’s true. 

My other concern is that providers will start to overly rely on the AI system, and not use their own clinical knowledge for context or to fact check the information. 

A 2025 study by researchers at the Massachusetts Institute of Technology (MIT) found that people who relied on ChatGPT to write essays had lower brain activity than those who used their own intelligence. Those who used AI alone became dependent on it and struggled when asked to perform tasks on their own.

Time will tell how Mayo Clinic’s AI chatbot will perform and how accurate it will be. Let’s just hope no patients get hurt while they figure it out.

Sicker Americans More Likely to Misuse Medication

By Pat Anson

What makes someone “misuse” a medication? Does it mean they’re addicted? Are they trying to get high? Do they have a substance use disorder? 

The answer may simply be that they’re depressed about being sick and want to feel better. 

That’s according to a new study that found that the misuse of prescription drugs is closely tied to the number of chronic conditions a patient has. Previous research has linked chronic pain to higher rates of opioid misuse, but researchers at Syracuse University found the overall disease burden plays a bigger role than whatever medication a patient is taking.

“We talk about the overdose crisis in epidemic terms,” says Andrew London, a Professor of Sociology at Syracuse. “It affects some populations more than others. We wanted to broaden that narrative a little bit and talk about prescription drug misuse more generally, because it’s not just prescription opioid misuse.” 

London and his colleagues analyzed data from the National Wellbeing Survey, an annual survey on the health and well-being of working age adults in the United States.

Nearly 33,000 respondents self-reported whether they were diagnosed in the last 12 months with hypertension, high cholesterol, diabetes, heart disease, obesity or being overweight, chronic obstructive pulmonary disease, post-traumatic stress disorder, traumatic brain injury, depression or anxiety. 

They were also asked whether they misused prescription opioids, tranquilizers, sedatives, or stimulants. Misuse was defined as someone taking a medication that was not prescribed to them or taking it in a way a doctor did not intend, such as taking a higher dose or taking a dose more often than prescribed.

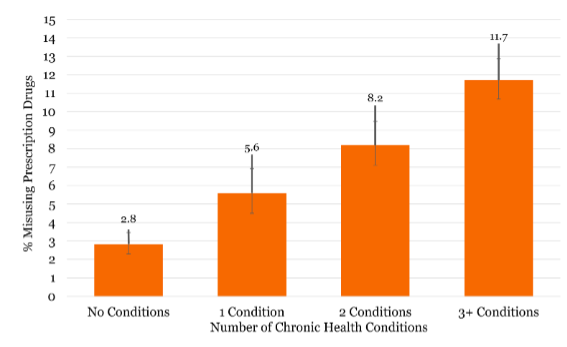
The study findings show that people with no chronic conditions had a 2.8% chance of misusing a medication. The risk doubled to 5.6% for those with one health condition and kept rising from there. People with two conditions have a 8.2% chance, and those with three or more conditions have a 11.7% risk of misuse.

Prescription Drug Misuse by Number of Chronic Health Conditions

source: SYRacuse university

“This simply tells us that the more conditions an individual manages, the higher the likelihood of misusing medications,” lead author Esther Oshaji, a doctoral student, said in a press release.  

People with anxiety, depression and other mental health conditions reported more misuse than those with physical health conditions, such as obesity or diabetes. Knowing that in advance could help healthcare providers develop more targeted treatments for patients at greater risk of misuse.

“It helps us to know that anxiety and depression are driving misuse among chronically ill patients,” Oshaji says. “Given that it is widely assumed that people misuse drugs because of physical health problems and chronic pain, it is important to show that depression and anxiety are actually driving misuse rates more than physical health conditions.” 

Misuse may also be driven by the number of doctors a patient sees or the number of prescriptions they have. People with multiple health conditions often have more access to medication, and may be more likely to try and manage their symptoms by taking less or more than what’s prescribed to them.

“Management of chronic disease requires active decision-making, so people make choices about how they’re managing doctors’ orders,” London says. “We know that patienthood, self-medication and agency are probably part of the story.”

A weakness of the study is that drug misuse is self-reported, and someone may be less likely to admit they misused a medication. Misuse is also a broad term that includes not using a medication because it’s not effective, no longer needed, or has too many side effects. Simply not taking a drug could be called “misuse.”

Misuse is also frequently confused with abuse, which is when someone uses a substance to get high or for self-harm, leading to negative consequences in life. 

Researchers at Syracuse are now studying whether chronic disease burden is associated with illicit drug use, including marijuana, and whether misuse is associated with gender, age, socioeconomic status and education. 

Hiding Your Chronic Pain Can Backfire

By Crystal Lindell

When I first developed intercostal neuralgia in 2013, I was so undermedicated and in so much pain that hiding my physical deterioration was not an option.

On work trips, I would lay on the floor behind our magazine booth in conference centers crying. Back in the office, I would sob as I typed out emails at my desk.

And I would talk openly with colleagues about wanting to kill myself because the pain was so severe.

It was the same at family events and social gatherings. If I showed up at all, I would lay on a couch in the back of the house for most of the party, tears streaming down my face because I was in too much pain to even sit up right. I would hardly interact with anyone.

And I would openly tell everyone there how I only made it because I took 20 mg of Norco before I left the house — and I’d be taking 20 more in a couple hours.

I was in a lot of pain, and I made no effort to hide that from anyone.

But then, as medication helped me get my pain slightly more under control, and as I learned coping strategies like pacing and forcing myself to stay calm, I started to find it easier to just hide what I was going through.

Unfortunately, I fear I may have now gone too far in the other direction.

The thing is, I saw firsthand how many people recoiled at my pain. They hated it, and by extension, they started to hate me. 

Visible physical pain — especially the kind that never seems to go away — makes people lash out, or worse, pull away completely.

In fact, when you’re in so much physical pain that people are forced to bear witness, they usually decide it’s easier to cover their eyes and pretend you don’t exist.

So, I changed my approach. When I interacted with people in real life, I did my best to pretend to be pain-free.

I loaded up on opioids, anti-inflammatories, and whatever else I could get my hands on, and plastered a smile across my face. I stopped talking about my health issues during polite conversation, and I made sure that if I had tears streaming down my face, it was only after the event, alone in my car.

Unfortunately, I’m sad to report that this has all been extremely effective. People are nicer to me when they think I’m healthy. More professional opportunities have opened up for me. And I have made more friends.

But now, all these years later, I’m starting to wonder if trying to completely hide my chronic pain is also, maybe, a mistake?

Because my chronic pain is very much a part of who I am, and it means that I make heavy sacrifices to show up with a smile on my face.

It means that if I want to get through a 7-hour work shift, I have to sleep for 13 hours before I go in. And then I have to sleep for 13 more when I get back home.

It means that I’m constantly counting out pain pills, and making sure I’m dosing at just the right times so that I’m at my peak when it’s most needed.

It means that a lot of the money I earn is going to medical bills, prescriptions and treatments.

It means that I’m often showing up after being awake all night in pain. And that every hour I give to a colleague or a friend has to be paid for with three hours of rest. 

It means I lose time with my fiancé when I am finally at home, because I physically can’t get out of bed.

Sometimes, I wish I could find a way to explain that to people. I wish I could tell them how much work it takes for me to show up so that they don’t take it — or me — for granted.

Then again, maybe I’m kidding myself in thinking that it even matters. If they really knew how much of a sacrifice I was making to walk through the door, maybe that would just make things worse. It would just make them more uncomfortable, more annoyed, and more avoidant.

I’ve been living with debilitating chronic pain for more than a decade, and I still haven’t found the perfect balance with all this. I still struggle with how open I should be about my health issues, and how much I should hide. 

I still don’t know how to make people understand, or care.

Perhaps I never will. 

In the end, all I can really do is be a person who understands and who cares. 

I have developed a reputation recently for being “super nice” and “caring so much.” I know it’s not always meant as a compliment, but I always take it that way regardless. 

I know what unrelenting pain does to a person, and as such, I also know just how much of an impact it can have when someone, anyone, shows even the slightest bit of empathy for what you’re going through. 

So being nice is the least I can do. 

Financial Anxiety Makes Medical Procedures More Painful

By Pat Anson

The high cost of healthcare is a big problem for many Americans. A KFF survey recently found that about one in four U.S. adults are “very worried” about paying for healthcare, and have skipped or postponed seeing a doctor in the last 12 months because of the cost. 

But rising medical costs do more than damage a patient’s bank account. New research shows that financial anxiety about the cost of healthcare may cause more physical pain during medical procedures, driving many patients to skip appointments altogether.

The study, “Paying for Pain: How Healthcare Costs Influence Physical Pain Predictions,” found that financial distress spills over into sensory expectations. That discomfort leads the brain to anticipate significantly more physical pain from procedures ranging from simple blood draws to complex endoscopies.

"We found that the psychological pain of paying money doesn't stay separate from our physical expectations," said lead author Helen Colby, Assistant Professor of Marketing at The Tepper School of Business, Carnegie Mellon University.

"When a medical test costs more out of pocket, people mentally brace for a more painful physical experience. Financial anxiety changes how we construct the prospect of healthcare in our minds before we ever set foot in a doctor's office.”

Colby and her colleagues conducted three experiments to see if the anticipation of an out-of-pocket expense for a routine medical procedure would heighten pain.

Three hundred adult volunteers were recruited for an imaginary blood draw. About half were told that their insurance would fully pay for the procedure, while the other half were told there would be an out-of-pocket cost of $53.  

Those who were told they’d have to pay reported significantly greater financial anxiety and anticipated physical pain than those who had zero out-of-pocket expenses.

In another experiment, 350 volunteers were told to imagine getting an endoscopy, a procedure that involves a thin flexible tube with a light and camera being inserted into the body to diagnose or treat a health issue. Half were told that insurance would pay for the endoscopy, while the other half were told there would be $787 in out-of-pocket costs.

The group that would have to pay for the procedure had significantly more financial anxiety. They were also less likely to schedule the endoscopy.     

For the third experiment, 400 people were recruited to be evaluated for a nerve condition. Half would pay nothing for the procedure, while the other half were told they’d have to pay $1,120 in out-of-pocket expenses.

Once again, those who anticipated paying a high cost had significantly more financial anxiety and were less likely to schedule the procedure.  

Since these were all “imaginary” procedures, we don’t know with certainty how physically painful they might have been in real life. But researchers say their experiments demonstrate that the cost of a procedure consistently predicts when patients have more financial anxiety, anticipate more pain, and are less likely to schedule appointments.

"Healthcare providers and marketers need to realize that price tags carry heavy emotional weight," Colby said. "Communicating lower-cost options, offering clear payment plans, or framing preventive care as low-cost can lower financial anxiety. By reducing the pain of payment, we can decrease expected physical discomfort and encourage patients to get the medical care they need.

Researchers say their findings suggest that pharmacies, vaccine makers, insurance companies, and public policymakers should market preventive care procedures like flu shots as being free or low cost. Consumers are less likely to seek treatment when procedures are more expensive, not only due to financial concerns, but also due to anticipated physical pain. 

Older Adults Should Be Cautious About Health Advice from Chatbots 

By Robin Brewer

It’s easy to stereotype older adults as tech-averse or novice tech users. Yet a growing number of adults age 60 and older are embracing artificial intelligence (AI), using it for entertainment, planning trips and even accessing health information.

I study how people interact with computers and technology – and specifically, how older adults use voice assistants and AI-powered chatbots like Amazon Alexa and ChatGPT to engage with information. 

Using AI for health information can be particularly fraught because chatbots can be so helpful in explaining complex medical information, but also risky if users automatically trust the responses they receive. That’s apparently what happened to a young woman in Seattle, who died after ChatGPT encouraged her to stop taking her epilepsy medication.

My research suggests that the most productive way of engaging with health information generated by an AI chatbot is from a position of informed skepticism – that is, remaining open-minded, yet using built-in features to evaluate the credibility and quality of chatbot responses.

The AI Appeal

About 1 in 5 adults turn to AI chatbots to ask questions about health, according to a 2025 survey of 300 adults. Questions might include asking about symptoms or seeking advice about diet and fitness. The chatbots might be mainstream services such as Claude, Gemini, ChatGPT or systems designed for a specific health provider.

People turn to these tools for many reasons. It can be easier to talk to a chatbot about sensitive topics, and chatbots reply almost instantaneously – much quicker than making an appointment to see your doctor weeks or months down the line. Chatbots can also explain complex topics in new ways and condense an overwhelming amount of information into a simple summary.

Although older people may be less likely than others to use AI, I’ve found in my own work that older people often use voice assistants like Siri and Alexa to ask health questions. Similarly, a poll I conducted with colleagues in 2025 shows that 1 in 2 older adults report using AI chatbots or voice assistants, and about 14% of people in this group are accessing health information.

Older adults often experience more health needs than younger adults due to long-term chronic health conditions or new age-related diagnoses. More health needs often means more health-related questions.

AI is particularly appealing for health questions because people get answers faster than searching across multiple websites when using a search engine – or having to wait for a healthcare visit. 

Moreover, being able to use chatbots and voice assistants at home can make people feel more in control of their health, compared with clinical settings where older people’s autonomy can be overlooked or where they may experience being excluded in lieu of conversations with caregivers.

What Are the Risks?

Although older people may use chatbots to supplement or replace medical professionals, AI use has risks.

For example, it can provide incorrect advice in medical emergencies, misclassify health conditions and be overly agreeable, responding with what it deduces the user wants to hear, even if the response is not factually accurate. AI experts call this last tendency “sycophancy.”

But these inaccuracies can be hard for a user to detect. AI-powered chatbots draw on vast amounts of data and use pattern-matching to predict words most likely to come next in a sentence. That means the output can appear correct but contain inaccurate information.

Most mainstream chatbots include a warning under the dialogue box noting that their output might contain mistakes, but it is often in small or gray text, making it easy to overlook. The warning is meant to encourage cross-checking information with published sources, but users rarely do so. In the 2025 survey mentioned above of 300 adults who used a health chatbot, 4 in 5 admitted they never verified its output.

In my own research, I found that older people searching with a voice assistant preferred to begin and complete their search process on the same device, suggesting they are unlikely to verify an AI chatbot’s output if it takes them to a different format. In contrast, younger adults expected AI to be a step in the search process, guiding them to seeking further information with the help of another option, such as a search engine. This difference makes it critical to provide strategies to older people as they use AI.

Another risk is privacy, since AI companies that make public chatbots often keep user prompts for training future models. Researchers generally recommend that users not include personally identifiable information when asking questions to chatbots.

Strategies for Safer Searching

Awareness that older adults may use AI in ways distinct from other demographic groups – and may encounter specific challenges – is growing. A bipartisan bill, the Aging with AI Act, introduced in the U.S. Senate in 2026, for example, underscores the need for more research on both its benefits and its risks.

My research points to a few guidelines to start with:

Learn how to opt out of AI. Although mainstream chatbots like ChatGPT are popular, the most common way people access AI is through a search engine because AI features are often built directly into search results. Some search engines, like Microsoft’s Bing, ask people to opt into using AI. Others, like Google Search, rely on users to opt out of AI.

Google shares an AI-generated summary at the top of each search result. To opt out when searching for information using Google, adding “-ai” to the end of the search query will remove AI content. Opting out of AI might be useful when searching for particularly sensitive health information that you wish to keep private.

Use the information quality features. Most AI chatbots have features that allow users to confirm the source of its output. For example, Claude, Gemini and ChatGPT include links to sources they used to predict the response. Make sure you explore these sources to confirm they are legitimate and to get more details that can help you find the information you need.

Further, you can change the model the chatbot is using, which can change how much depth the chatbot goes into in its response. For example, Gemini has a drop-down menu next to the search box that includes “flash-lite,” “flash” and “pro” models. Chatbots’ more advanced versions provide more thorough responses that can help users better determine information quality.

And users can report inaccurate, toxic or harmful content by clicking the thumbs down icon shown at the bottom of the response.

Ask better questions. Ask for objective information that can be verified, rather than subjective advice, particularly in high-risk health contexts. For example, instead of asking “which high blood pressure medicine should I take?” ask “what are the side effects of” a particular high blood pressure medicine.

And to prevent sycophancy, phrase questions neutrally. For example, instead of asking “Is it a good idea to get a flu shot?” a searcher can instead type “Tell me about the pros and cons of getting flu shots.”

Don’t use AI as a replacement for medical professionals. Health-related chatbot output is best used collaboratively with a medical professional. This might include saving the chatbot output to discuss during your next healthcare appointment, using chatbots to understand complex diagnoses from your doctor, or getting a chatbot to suggest questions to ask your doctor during your next visit.

Most importantly, confirm health-related answers that result in making changes to your health routine with your healthcare provider. A knowledgeable, licensed healthcare provider is best qualified to determine how general information about illness or treatments would apply to your specific situation.

Robin Brewer, PhD, is an Associate Professor at the University of Michigan in the School of Information. Her research covers old age, disability, and technology use. 

This article originally appeared in The Conversation and is republished with permission.
