
Do Native Americans Need a Pain App?

By Crystal Lindell

The University of Oklahoma has received a $3.4 million dollar federal grant to help Native Americans with chronic pain – and they’re going to spend all of it on an app.

The money, which is coming from a five-year National Institutes of Health grant, will go towards building the first chronic pain mobile health (mHealth) app designed by and for Native Americans. Nearly one in three Native Americans live with chronic pain, more than any other segment of the U.S. population.

In a news release about the project, the university makes clear the app will only provide behavioral and psychological assistance for pain, because “medications, while commonly prescribed for chronic pain, are also easily abused.” 

Neither of those things are true. Many Americans with chronic pain find it nearly impossible to get opioid pain medication, so they are definitely not “commonly prescribed.” And most pain patients do not abuse their medication.

The researchers referenced our country's history of horrific treatment of Native Americans — including the fact that Oklahoma was the end of the Trail of Tears — to justify this whole endeavor.

“Native American communities have experienced intergenerational trauma, and they continue to experience contemporary traumas,” said Jamie Rhudy, PhD, a professor in the OU Department of Health Promotion Sciences. “These are the types of experiences that can place our brains on high alert and amplify pain.”

It’s infuriating to read that rationale, knowing that programs like this only serve to keep an effective pain treatment away from people who need it: opioids.  

Researchers say the app will focus on things like stress management, anxiety, sleep hygiene, physical health and diet.

“All of these can be drivers and amplifiers of pain,” said Rhudy. Then, in a quote only someone without chronic pain would say, he added this:

“Chronic pain is largely a construct of the brain. We’ve been taught that we have pain because maybe our joints wear out, or we have tissue damage, but everyone experiences pain differently, which our mHealth therapies will recognize and respond to,” said Rhudy.

In short, it’s all in your head.

Then he adds: “Sleep, stress and discrimination are not variables easily targeted by medications, but they do respond well to targeted psychological and behavioral interventions.”

Actually, as a chronic pain patient myself, I can tell you that sleep and stress are both easily targeted by medications. It’s just that many of those medications are controlled substances that have been blamed for our nation’s drug problem.

We asked Tamera Lynn Stewart, an Oklahoma patient advocate, what she thought of the app. She’s glad it's being developed with direct input from Native Americans, but says it “misses the mark pretty badly” in removing barriers they face in getting pain care.  

“My problem isn’t that they’re offering behavioral tools; it’s that we’ve spent years restricting, stigmatizing, or taking away treatments that actually help people, and now we’re approaching an already underserved population with an app while heavily emphasizing discrimination and psychology as drivers of their pain,” said Stewart, National Director of the P3 Alliance, a patient advocacy group. 

“We say they are disadvantaged in receiving quality care for their pain without admitting much of it was caused by the same policies incentivizing this study. All while forgetting to mention that many historical and current drug war policies criminalized or removed the very tools the indigenous population once relied on to treat their pain.” 

Stewart is worried that a pain app designed for a very specific high-risk population will eventually be deployed as a treatment for everyone else – something the pain community has seen before.

“I’m all for adding options. I’m much less enthusiastic when ‘adding an option’ starts looking like another way to redefine the problem so the healthcare system can offer less actual care,” Stewart told PNN.

After building and testing the app, OU researchers plan to have a randomized controlled trial to see how well it works.

“With the team we have in place we’ll be able to bring all the necessary components together to develop, test and deploy a novel, culturally tailored chronic pain intervention that will be scalable,” said Rhudy.

I will definitely be keeping an eye out for the trial results – especially if the app is then pushed on the larger chronic pain community. I’ll be especially interested to see how effective the app is compared to opioid pain medication – although I doubt they will include any data on that.

It’s so disappointing to see money and energy going to projects like this, which are clearly a result of opioid-phobia. Every time a project like this is funded, it means less money and effort going toward interventions that probably have much a higher chance of actually helping people in pain.

How a Professional Advocate Can Help Patients

By Jennifer Schlinger 

Imagine your mom has just been discharged from the hospital to a rehabilitation center after hip replacement surgery. She has the paperwork, the facility’s address – and a long list of questions. 

Will her insurance cover her entire rehab stay? Does she have enough pain medication until she gets settled? Will the hospital transfer her prescriptions? Are they accurate?

Scenarios like this are exactly what patient advocates are trained to help with. They understand patients’ and families’ concerns, ensure their voices are heard by medical staff and interface with care teams, insurance companies and facility administrators. They also coordinate care, set up follow-up appointments and address potential gaps or blind spots in care.

I train social workers – who often serve as patient advocates – to help people in a variety of settings, including hospitals and nursing homes. Earlier in my career, I served as a professional patient advocate supporting people in hospitals, home health and hospice.

A trained patient advocate can provide much-needed support for people on their healthcare journey. Here’s what you need to know to work with one most effectively.

The Evolving Field of Patient Advocacy

Patient advocacy emerged out of the Civil Rights Movement’s focus on individual protections and rights. In 1966, healthcare advocacy pioneer Ruth Ravich founded the Department of Patient Representation at Mount Sinai Hospital in New York – widely considered the beginning of the patient advocate role.

Historically, doctors made decisions for patients without fully involving them in their own care. But during the 1960s and in subsequent decades, a growing patient rights movement embraced the importance of informed consent for honoring patients’ autonomy. Patient advocates arose as an important voice in this movement by educating patients about their rights and helping them participate more fully in decisions about their healthcare.

For decades, “patient advocate” was a self-described title, not a standardized role. As the healthcare system became increasingly complicated, the need emerged for national standards on skills, ethics and best practices. In 2018, the Patient Advocate Certification Board established basic requirements for patient advocates and created a professional certification, which is the only one available for this role in the U.S.

Certification is not required to be a patient advocate, but it indicates that a person has received specific training for the role. To become certified, patient advocates must pass an exam demonstrating a knowledge of health and medical concepts, issues relating to paying for care, an understanding of the healthcare system, how to work collaboratively with patients and other areas of competency. They must complete continuing education to maintain certification.

Some healthcare professionals who serve as patient advocates are not certified and instead have learned relevant skills through their education or professional experiences. They may work in rural healthcare facilities, for instance, where they wear multiple hats as nurses or social workers who are also advocates.

What Does a Patient Advocate Do?

Patient advocates are trained to support, inform and guide patients through the healthcare system. They help explain medical information, such as a medication’s side effects or treatment options. They also make sure patients’ questions are answered and their concerns are addressed.

When a patient receives a referral to a specialist, a patient advocate can connect care across various healthcare providers, making sure details about the patient’s condition or care priorities don’t fall through the cracks and helping to arrange transportation to appointments.

Early in my career, for instance, I worked at a hospital with patients who were being discharged to their home or to a long-term care facility. I started by understanding each patient’s goals, assessing their living arrangements and the type of care they needed and identifying any concerns they had about their discharge plan. 

Before they left the hospital, I coordinated community support or additional care they might need, such as home-delivered meals, home healthcare, and physical, occupational or speech therapy.

Patients often have family members who are advocating on their behalf – and family support is invaluable. Working with a patient advocate can provide something different: a grounded, objective perspective, expert knowledge of the healthcare system and knowledge of resources that patients and family members may not be aware of.

Indeed, patient advocates interact closely with family members and friends who are involved in the patient’s care. As liaisons between the patient, family and healthcare providers, their job is to keep the patient’s needs, preferences, goals and values at the center of their care.

Working with a patient advocate can help patients feel more confident in making informed decisions. According to a 2023 survey by a nonprofit alliance called the Coalition of Healthcare Advocacy, 92% of patients and healthcare providers reported that working with a patient advocate positively affected patients’ care.

Understanding Bills and Insurance Coverage

Managing financial aspects of healthcare can be overwhelming for patients and family members, particularly in the midst of a health crisis. Medical bills are often impenetrable documents littered with complex codes and terminology, and sorting through charges and details about insurance coverage can feel intimidating, if not downright paralyzing.

A patient advocate can provide a knowledgeable outside perspective on these issues that’s not clouded by the urgency and emotional weight of illness.

Some patient advocates have specialized knowledge in medical billing, coding, insurance and other financial matters. They can answer questions about medical terms or clarify charges on a patient’s bill, review the bill for errors such as incorrect or duplicate charges and assist with figuring out insurance coverage and reimbursement.

A healthcare advocate can help make sure that patient’s needs, preferences, goals and values remain at the center of their care.

If necessary, they can also appeal claims by acting as a liaison between the patient, the healthcare facility and the insurance company. Patient advocates can also help patients work with a hospital to set up a payment plan, explore additional financial support or coordinate access to community resources.

If a finance-related question falls outside an advocate’s knowledge or expertise, they can help the patient identify the right people to talk to.

Finding and Working with a Patient Advocate

Finding a patient advocate is not always as straightforward as it should be.

If you are unsure where to start, ask to speak with a hospital social worker or case manager. In some cases, an advocate’s services are provided by the healthcare organization or are covered by insurance, but in others, the patient or family must pay for them out-of-pocket.

Many healthcare facilities, including Veterans Affairs, have patient advocates on staff. You can contact your local hospital or clinic and ask to be connected to their patient advocate. 

Alternatively, you can search for a patient advocate in your area through the Centers for Medicare and Medicaid Services website or the National Association of Healthcare Advocacy.

If a certified patient advocate is not available within your healthcare facility, request to speak with a social worker. Social workers have the education and expertise to support patients and families, to connect them with resources and to advocate for patients’ needs.

Before meeting with a patient advocate, identify your main objectives – for example, preparing for a transition home, clarifying a treatment plan or understanding medication changes. Then, write down your main concerns and questions. The Care Partner Project offers checklists for questions to ask healthcare providers, prepare for doctor visits, evaluate senior living communities and more. Gather any relevant information, such as medication lists, medical records, insurance documents and medical bills.

When you meet a patient advocate you’re considering working with, you can feel out whether they are a good fit by asking about their professional background, areas of expertise, experience and credentials. Some questions you might start with include:

  • What is your experience with cases like mine? (For example, patients being transferred to a rehabilitation center, if that is your situation.)

  • Can you provide an example of how you helped a patient or family work though a difficult healthcare situation?

  • How do you typically communicate with patients and families, and how often can I expect to hear from you?

  • How do you help patients speak up about their concerns and preferences to their healthcare providers?

Finding a healthcare advocate you trust can make navigating a complex health situation much less overwhelming.

Jennifer Schlinger, PhD,  is a Clinical Associate Professor of Social Work at the University of North Dakota

This article originally appeared in The Conversation and is republished with permission.

I Was Shocked How Effective Shockwave Therapy Can Be

By Madora Pennington

I have an old knee injury. You probably have one, too. 

Or maybe it’s your hip, ankle or elbow.  Something that flares up from time-to-time and makes you say in frustration, “This old thing. Again?”

Decades ago, I slipped. Wearing heels as I was climbing into an SUV in the rain, my kneecap came down on the running board, stretching out the tendon. My knee swelled to the size of a baseball. Tendons stretched like that do not snap into their old shape. I have been limping ever since.

There is no simple surgery for a patella alta (high kneecap) injury. Over the years, I tried physical therapy, knee braces, taping the kneecap in place, prolotherapy (sugar injections) and platelet-rich plasma injections (PRP therapy). 

All of those helped to some degree. But still my knee continued to bother me, often when I did activities that I love, like tennis and running. 

It became so annoying, I thought it was time to work on it again.

Healing Shocks That Reduce Pain

In looking around for new modalities, I found something I had never heard of: Extracorporeal Shockwave Therapy (ESWT).

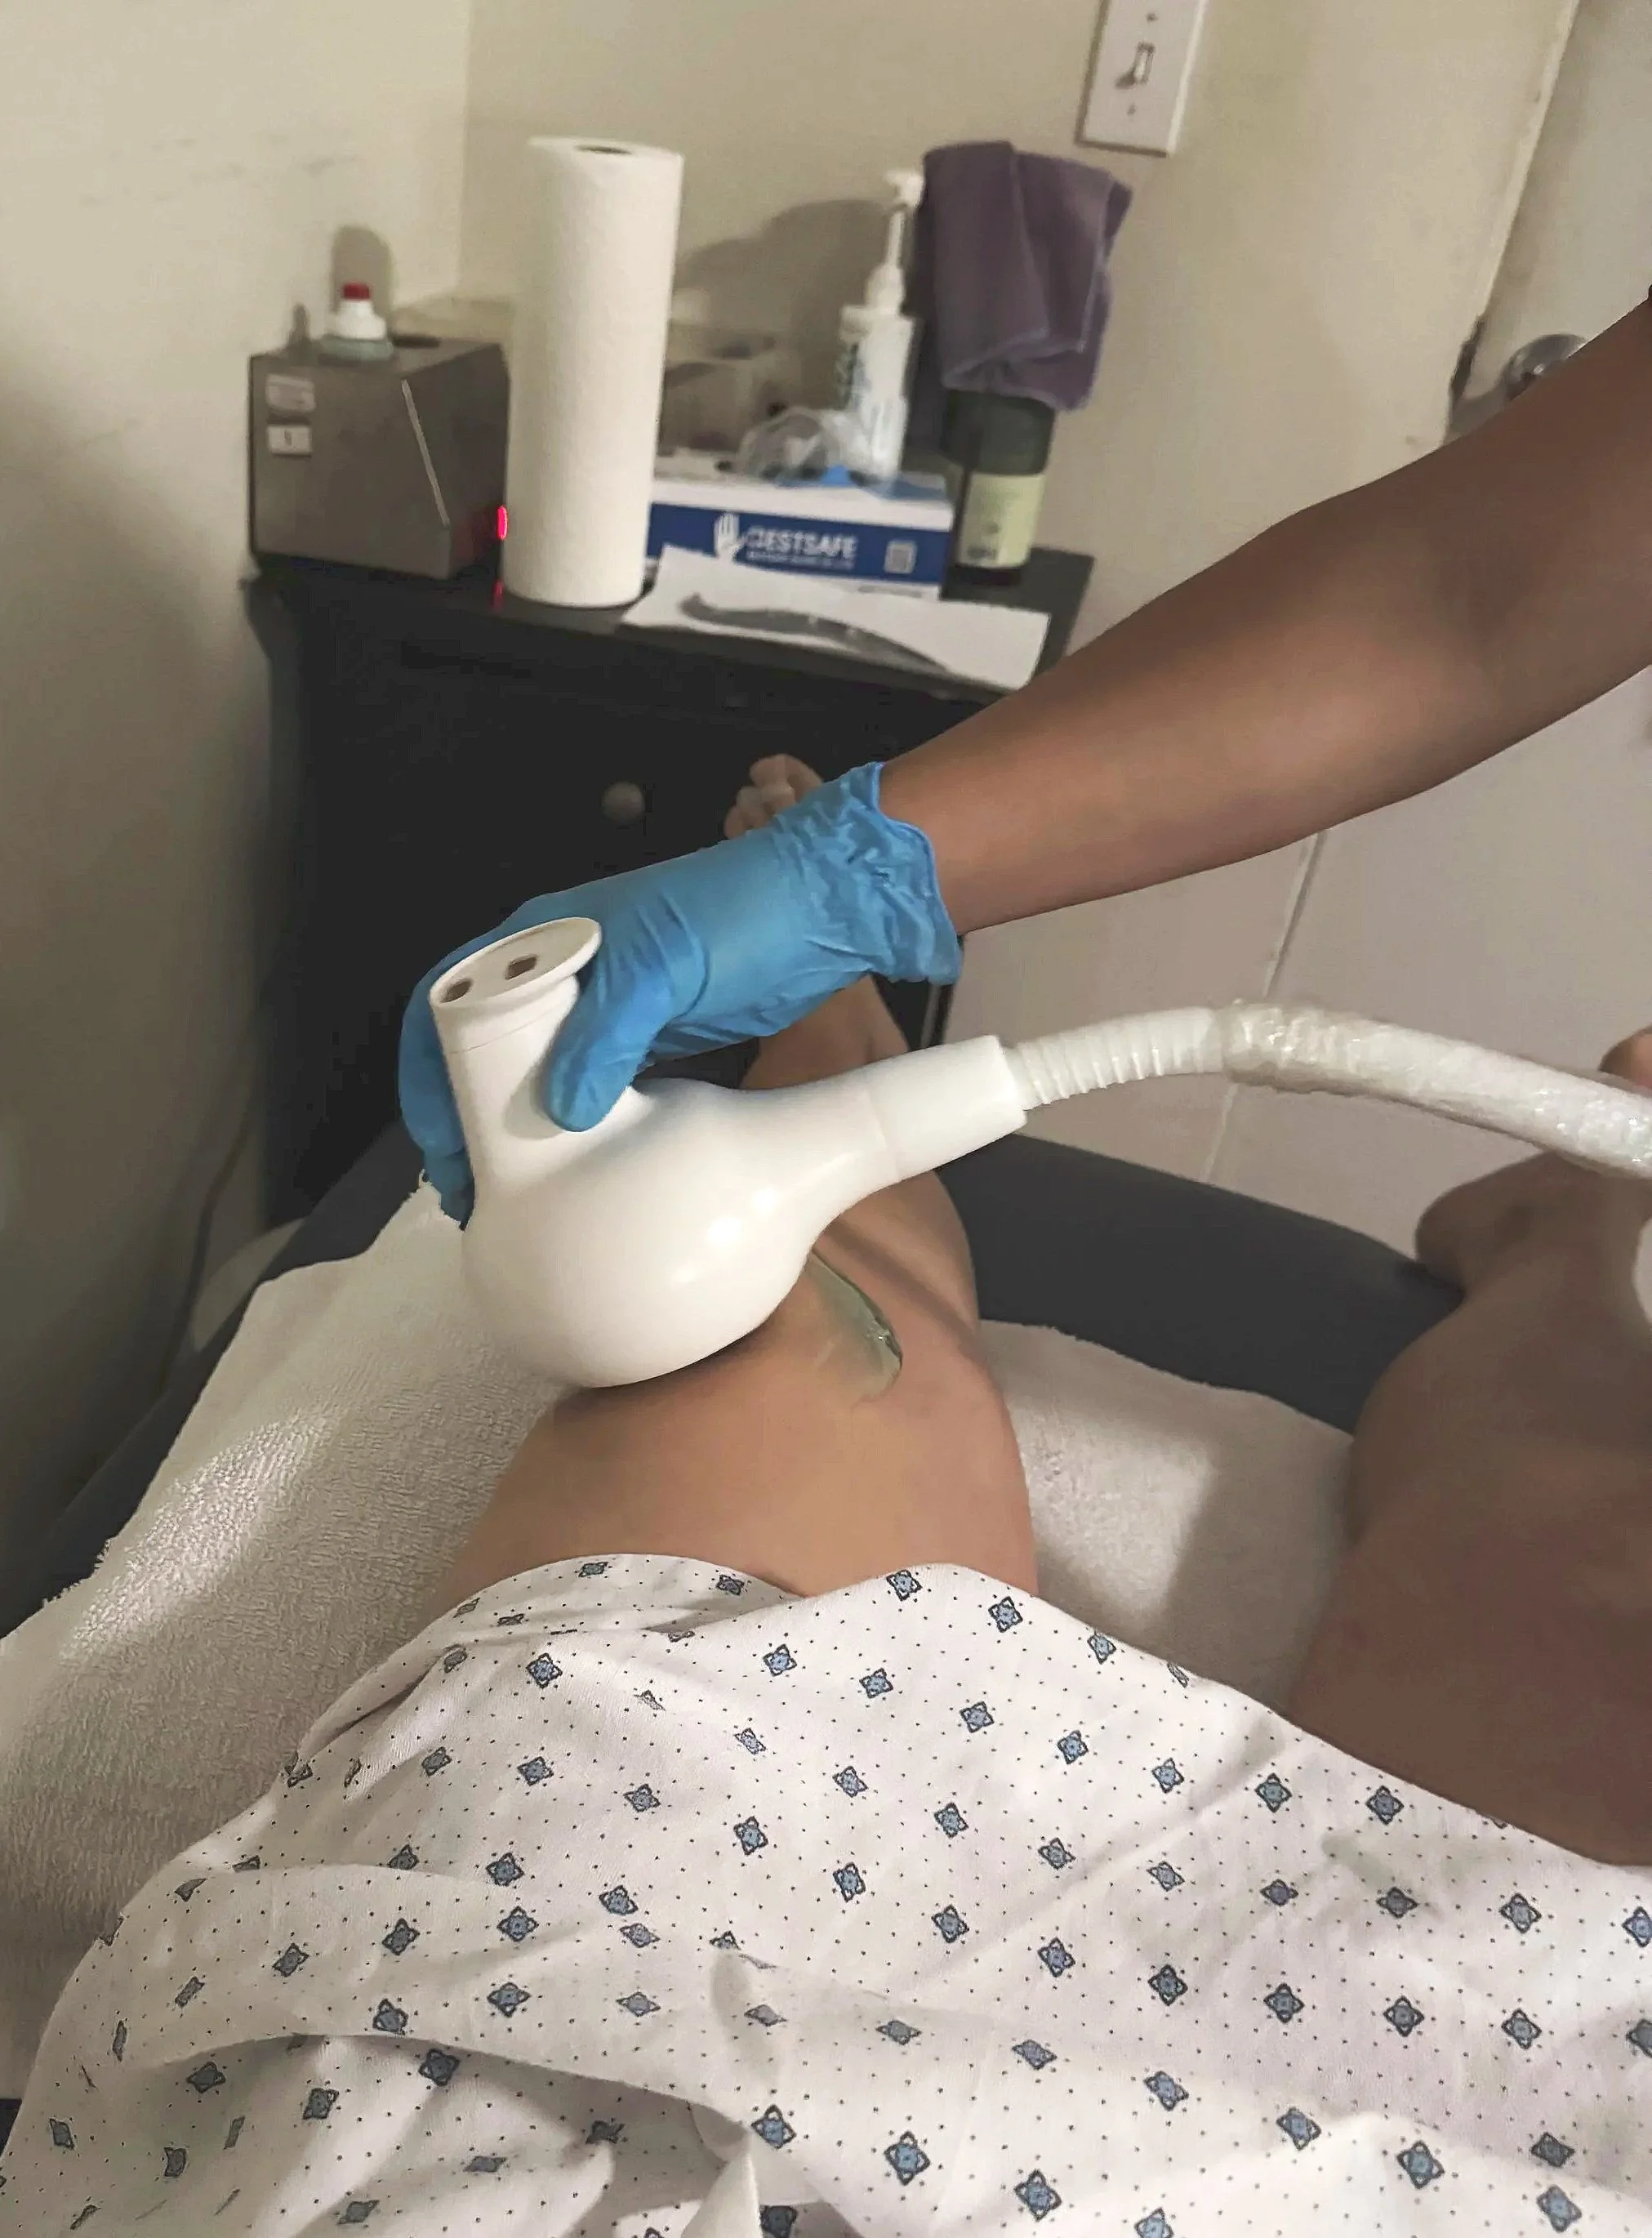
ESWT is a noninvasive treatment that uses a device applied to the skin near injured areas that emits high-energy acoustic sound waves that promote healing and repair tissue. 

Shockwave therapy was originally developed to break up kidney stones without surgery. Once shattered into smaller sizes, kidney stone fragments pass out of the kidneys easier and exit the body with the urine. 

The treatment on kidney stones was successful, but there were concerns that the shockwaves were so intense they might damage nearby bones. It turns out the shocks actually stimulate new bone formation. Later investigations showed that shockwaves at a different dose could also stimulate cellular regeneration in soft tissue. 

In 2000, the FDA approved a shockwave device for chronic plantar fasciitis (pain in the soles of the feet). And in 2002, the FDA approved another device for the treatment of tennis elbow, a repetitive strain injury common to tennis players.

Like nearly all technology, today’s ESWT devices are smaller, cheaper and easier to operate effectively. Most protocols suggest several sessions separated by about a week. Unfortunately, they are usually not covered by insurance.

ESWT can be used on a wide variety of conditions that would normally send a patient to physical therapy, such as tendon injuries, slow-healing bones, arthritis, calcific tendonitis of the shoulder, and more. 

Shockwave therapy can encourage bone formation, new blood vessels, growth factors, healing in tendon cells, and collagen remodeling, while lowering inflammation and pain signaling.

Shocking My Knee 

Studies on ESWT for a kneecap injury such as mine showed mixed results and were not very promising. But that did not deter me. 

I was happy to try something besides an injection, especially something that could reawaken dormant healing processes. Having physical therapy along with ESWT was also recommended, so I did that, too.

Shockwave therapy sounds like it could be painful. A few times during my treatments, it was. The tech can turn down the machine if the zaps are too much. Because stronger pulses are more effective, I tried to endure them. 

The shocks were oddly pleasant, giving me a bit of an adrenaline rush and immediate relief. The tech did not isolate her treatment to just the joint. She used it around the neighboring tissue and muscles.

After my second treatment, to my utter delight, going up and down many flights of stairs was easy for my knee. It actually felt good. My kneecap held firmly in place, not snapping around as it can. 

This was a faster, more significant improvement than any treatment I have had in the past.

I purchased a package of shockwave treatments and had more sessions to use, but my knee felt like it didn’t need any more shocks. So I switched to having ESWT on overworked areas that have helped my body compensate for the deficiencies in my knee. The overused muscles in my pelvis and neighboring hamstring helped keep me balanced as I unconsciously favored the injured knee.

The shockwaves flowing through my back and glute muscles were intense, but just as soothing as they were on my knee. I could feel them all the way through to my hip joint. The treatment lifted feelings of stress that I was not aware of, perhaps by allowing more blood flow around the nerves caught under all my musculoskeletal stress. 

This other-side treatment accelerated my physical therapy progress. In fact, my physical therapist’s assessment was that the knee itself was in good shape — it was the old compensatory muscle patterns that were causing me pain, like the shortened thigh muscle pulling the kneecap and causing discomfort. 

Those other modalities I pursued in the past may have been effective, but I never had the full course of physical therapy the injury needed until now. Perhaps this is why the studies I read recommend physical therapy in addition to ESWT in order to get the best result. 

Time will tell if my old knee injury and the package of dysfunction surrounding it can be resolved. I am optimistic. My tennis has never been better, as formerly tight, overworked muscles are free to support my swings. Running is not bothering my knee at all. 

I would try ESWT again on other unhappy joints and tissue in the future.

Should AI Be Used to Prompt People in Pain to Exercise?

By Crystal Lindell

We all know that being too sedentary contributes to poor health. It might even make your pain worse. But many of us still spend way too much time sitting in one place watching TV, scrolling on our phones, or working at a computer.   

“Individuals with certain chronic pain disorders face a paradox: they are at increased risk for sedentary behavior due to pain-related interference, even though significant gains in symptom relief and health benefits from increasing their PA (physical activity) for symptom management have been demonstrated,” says Ipek Ensari, PhD, who studies artificial intelligence (AI) and human health. 

Ensari and her colleagues at the Icahn School of Medicine at Mount Sinai wondered if wearable devices could be used to help women with chronic pelvic pain stand up and move around more. 

Their study, recently published in the journal Women’s Health, wanted to see if AI could predict when patients would have prolonged periods of inactivity. 

They recruited 134 women with chronic pelvic pain, primarily from endometriosis, along with 61 healthy women for a control group. Participants wore Fitbit devices for up to 90 days, generating minute-by-minute information about their physical activity, heart rate, steps, and sleep patterns.

"Our goal was to determine whether everyday wearable devices could serve as an early-warning system for prolonged sitting in women living with chronic pelvic pain," Ensari explained in a news release. 

"Rather than offering generic advice after the fact, we wanted to determine whether we could anticipate these moments and support people with simple, well-timed prompts that fit naturally into their daily lives."

The research team gathered data from each participant and developed personalized forecasting models to predict their activity levels one hour ahead of time. The goal was to identify 15-minute periods when a participant could stand up and move around, which the researchers called an “exercise snack.” 

Those short activity breaks may be more realistic and achievable than longer exercise periods, especially for people with chronic pain. The work also challenged the assumption that AI focused on health needs to be complex. Relatively simple AI models forecast prolonged periods of sitting just as well as complex ones.   

"We were surprised by how well the simplest models performed," said lead author Jannes Jegminat, PhD, a former postdoctoral research fellow at the Icahn School of Medicine. "More complex AI is not always better. Lightweight, interpretable models can accurately forecast sedentary behavior while being practical enough to run directly on a person's own device, which also helps protect privacy." 

Unfortunately, the research did not include any further investigation into whether or not participants would actually get up for a walk when prompted. And there seems to have been no consultation with pain patients on whether this technology is something they’d want and use.

The researchers admit that further study is needed to see if the AI prompts could actually help patients.

"This study suggests that predicting prolonged sitting is feasible, even if the individual has chronic conditions that might impact their daily routine," said Ensari. "The next step is determining whether delivering personalized movement prompts based on those predictions actually helps reduce sedentary time, improves symptoms, and enhances quality of life. Those questions will require prospective clinical trials."

It’s unclear how the technology would be applied to periods when someone needs to be sedentary, such as when they are working, eating, watching a favorite show, or in too much pain to move. 

The last thing I want to see on my AI watch as I’m driving late to work is a notification telling me to go for a walk instead.  

It’s becoming clear that anything and everything related to artificial intelligence is the new trendy topic for research, and it’s likely the topic is now also yielding better funding opportunities. But as researchers continue to study the ways AI can help us medically, they would do well to remember to ask patients for their input as well.

The work was funded in part by the Eunice Kennedy Shriver National Institute of Child Health & Human Development and by the Clinical and Translational Science Awards at the National Center for Advancing Translational Sciences. 

My Cats Help Me Cope with Chronic Pain

By Crystal Lindell

It is ironic that I was initially opposed to getting a cat because I have chronic pain.

I hate getting up early. I hate having to do anything right when I wake up. And I have no money.  

Cats wake you up at 5 am, expect to be fed immediately, and keeping them alive is expensive.

But when the mother of my fiancé Chris moved into senior housing, she was only allowed to take one of her two cats with her.

Thus, her long-haired tortoiseshell cat – affectionately named Princess Diana – had nowhere to go but to our house.

Although I was initially reluctant, Princess D quickly won me over when, on her first visit, she ran over to me while I was sitting in a rocking chair. She stared up at me with the eyes of a cat looking for love, and jumped up into my lap.  

I was hooked.

We became a one cat household.

Eventually, Princess D’s former sister Basil was also looking for a home, after Chris’ mom was no longer able to care for her either.

CRYSTAL WITH PRINCESS DIANA

Basil, a beautiful long-haired black cat, came with a pre-written warning for the vet, and lots of war stories. She was a scratcher. And a biter. If we hadn’t taken her, they were going to put her down.

Over the years, in the comfort and predictability of our home, Basil has softened. But just last week, she bit my arm because she got confused in the middle of the night.

We love her regardless.

After Basil came to live with us, we found our orange boy Goose and our brown tabby Goldie Hawn, outside. 

And when we moved in with my relatives, two gray-haired cats, Gracie and Cinnamon, joined our crew.

Yes, that brings the total to six cats. Yes, I know that puts me into crazy cat lady territory. But the thing about being a crazy cat lady is that I love them all too much to care what you think.

Just as I feared, they do all wake us up at 5 am, asking for food. And it does indeed feel like I’m pulling myself out of cement to get out of bed, just so that I can open a can of Friskies for them at dawn.

Truth be told though, having a reason – actually six reasons – to get out of bed every morning goes a long way when you’re dealing with pain that never ends. They give me purpose, and in return, I give them treats.

Having six cats also means that at least one of them is always willing to nap with me whenever I’m having a bad pain day. And naps covered in cats are healing. 

I confess, we do spend a lot of our money on our cats, especially after Princess Diana developed diabetes and almost died. We buy $140 vials of insulin every other month to keep her alive.

But she keeps me alive by giving me a reason to live, so really it all evens out.

In the end, our six cats give my life meaning, relieve stress, take my mind off my pain, and fill our home with love. All of those things go a very long way toward helping me cope with chronic pain.

In fact, there’s even data to back this up.  

In 2019, a National Poll on Healthy Aging conducted by AARP and the University of Michigan found that pets can offer their owners a wide range of health benefits.

The people surveyed said their pets helped them enjoy life (88%), made them feel loved (86%), helped reduce stress (79%), kept them physically active (64%) and helped them cope with physical and emotional symptoms (60%), such as taking their mind off pain (34%).

For those who said their health was fair or poor, pet ownership offers the most benefits. More than 70% of older adults said their pet helps them cope with life’s challenges, and nearly half (46%) said their pets help distract them from pain.

I used to think that having chronic pain was why I could never care for a pet. But I’ve come to understand that caring for a pet is one of those things that gives more than it takes. It’s because of my chronic pain, that having a pet – or six of them – is so vital to my well-being.

Less Is More: It Doesn’t Take Much Exercise to Reduce Pain

By Pat Anson

It won’t cure you or make your pain go away, but moderate levels of exercise could give you some relief from acute and chronic pain, according to a new study by Australian researchers.

In a systematic review of 157 clinical trials, a research team at Adelaide University found that less than two hours of exercise a week could reduce pain by about 1.1 points on the zero-to-ten pain scale. In fact, exercise of low intensity and short duration appears to be more beneficial than longer, intense workouts.

“Our study found that exercise was associated with substantial reductions in acute and chronic pain across all forms of exercise – whether that be via aerobic or resistance exercise, or through gentler movement such as yoga, Pilates or tai chi,” lead author Ben Singh, PhD, a Research Fellow at Adelaide’s School of Allied Health and Human Performance, said in a press release.

“Importantly, we found that more exercise wasn’t necessarily better. In fact, shorter-duration and lower-intensity programs showed greater reductions in pain, suggesting people may not need to exercise harder or for longer to experience meaningful benefits.”

The study findings, published in the journal PAIN Reports, show the most significant reductions were for pain caused by these conditions:

  • Axial spondylarthritis

  • Cancer

  • Musculoskeletal conditions

  • Fibromyalgia

  • Hip replacement

  • Low back pain

  • Migraine and headache

  • Neck pain 

  • Osteoarthritis

  • Idiopathic pain in older adults

  • Osteoporosis

  • Menopause

  • Pregnancy-related pain

  • Primary dysmenorrhea

  • Rheumatoid arthritis 

Low intensity workouts from tai chi, yoga and Pilates were beneficial, but the form of exercise that produced the largest reduction in pain was a bit of a surprise: Dancing.

That finding, however, is based on a single study of dancing by fibromyalgia patients and should be taken with caution. “Although dance-based interventions may offer promise for this population,” researchers say further studies are needed to prove the effect.

There are four key reasons why exercise has an analgesic effect.

First, exercise stimulates the release of endogenous hormones (endorphins), which act as natural painkillers and increase pain tolerance.

Second, exercise enhances the production of neurotransmitters such as serotonin and norepinephrine, which play crucial roles in mood and pain modulation.

Third, exercise reduces systemic inflammation, a common driver of chronic pain, by modulating immune system function.

Finally, exercise activates the body’s endocannabinoid system, which helps to modulate pain perception, mood, and inflammation.

“When we exercise, our body releases chemicals including endorphins and serotonin that can help reduce how strongly we feel pain and increase our pain tolerance,” Singh explained. “Additionally, it helps calm inflammation and change the way our brain responds to pain, while also improving mood.

“These effects help explain why exercise can be such a powerful tool for pain management. Yet despite the evidence, it isn’t used as routinely as it could be and is rarely prescribed with the same precision as medication.”

The idea that exercising less than 2 hours a week is more effective runs counter to many current exercise guidelines, which recommend 150 minutes or more per week. That amount can feel unattainable for many people with chronic pain. Shorter, less intense physical activity is more realistic and may help people overcome their resistance to exercise. 

“These findings support starting with manageable, lower-dose (exercise) programs to build confidence, promote adherence, and reduce fear of symptom flare-ups, key barriers for people with chronic pain,” researchers concluded. 

“Exercise should not be considered a universal solution or expected to eliminate pain entirely. Its efficacy will depend on individual factors such as the underlying pain condition, level of physical function, and adherence.” 

Mourning the Loss of a Healthy Body

By  Li-elle Rapaport 

Body changes can raise disturbing feelings, such as looking in a mirror and seeing a reflection that may feel spiritually empty, unproductive, ugly or weak.

Unpleasant sensations such as pain, pins and needles, soreness coursing through limbs and an inexplicable fog filling the head are a reminder that this body is not the same you anymore, prompting us to wish there was a way to get back there. It may feel impossible to live well unless you do.

This is the disillusionment that most of the population will face at some point in life, through aging, chronic pain or invisible illness (a disease or health problem that cannot be externally seen, including autoimmune diseases, chronic pain and fatigue, and recently, long COVID).

Recent global estimates suggest one in five people are currently experiencing chronic pain. The most prevalent chronic pain reported by adults ages 75 and over includes low back pain and migraine, while tension-type headaches are more often experienced by younger adults. Chronic illness (diabetes, heart disease and other mid-to-late-life diagnoses) affects about three-quarters of the world population.

Despite how common chronic illness is worldwide, the nuances of navigating a changing body are not often discussed. It’s time for an honest, evidence-based conversation about what it means to navigate chronic pain and illness, aging and transforming identity post-diagnosis, and how to grieve this loss and maintain meaning through these changes.

Why It Matters

Research suggest that those with internalized stigma of chronic illness are more preoccupied with how their illness detracts from their view of themselves, and also have a greater tendency to overlook positive aspects of life with a chronic illness.

Psychologists have observed how preoccupation with illness or pain is often accompanied by other grief behaviours. A 2025 study explored how Danish chronic illness patients navigated loss and growth. The study found that many with chronic illness find themselves mourning the life that they thought they would have, often leading to loss of motivation and joy in everyday life.

The perception of losing the life they had once envisioned is often accompanied by a focus on getting back to the “before illness” version of themselves as people struggle to accept how their body has changed, perhaps in how it looks but definitely in how it feels.

These changes and associated feelings of loss often permeate a person’s sense of identity, as well as their perceived roles within social relationships. Many report a fear of burdening others, especially loved ones, often describing feelings of guilt that “others have it worse than I do.” This is where internalized stigma festers.

Some people have also described feelings of anger, isolation, shame and exhaustion accompanying sadness. Meanwhile, others have expressed frustration over a gradual loss rather than a “clean break,” accompanied by the inability to find closure.

Making Sense of Grief

First, it’s important to understand why accepting this continuous loss feels so impossible. Theories of control in psychology state that humans desire control or the ability to achieve a desired outcome according to our own standards.

When that ability is seen as stripped away, people are more likely to experience negative mental health symptoms, like anxiety, depression and even grief. Specifically, feelings of diminished perceived control (subjective belief about our ability to achieve desired outcomes) occur when we face continuous roadblocks to living our desired life because of chronic illness.

One of the major consequences of loss and major life change is that it can disrupt meaning and challenge identity, purpose and assumptions about the future. At a time when people feel there is little they can control, psychologist Robert Neimeyer’s Meaning Reconstruction Theory poses the questions: “How do I move forward?” and “What matters most?”

While the original theory was proposed as an approach to coping with the loss of a loved one, the process is somewhat similar to grieving the close ally that is your body. This theory approaches grief by making sense of the loss and finding ways to rebuild a sense of purpose in a changed life (and body).

To answer relevant questions about how to move forward with chronic illness, two ongoing approaches are needed: integrating the loss and recentring purpose and meaning.

Integrating the loss may look like processing significant bodily losses in therapy, finding trusted loved ones to talk about the loss with and focusing on being realistic about your current body without judgment.

Second, recentring purpose during this major life change involves understanding your why: why is this loss so significant to you, why does it hurt? Maybe it’s because you love hiking in the mountains and a new diagnosis with arthritis feels like the end of this joy. Part of rebuilding meaning is finding new approaches to fulfilling this purpose — perhaps hiking may look different, but nature can be accessed and loved with chronic illness present.

Rebuilding meaning might also look like making meaning from this loss: What has this change taught you about yourself, about the impact you can make? Approaching present and future with this perspective helps process grief in a more protective way.

Living with chronic pain, illness and the changes that come with aging often involves grieving physical loss, but also shifts in purpose, relationships, identity and future plans. While these changes challenge our perceived control and purpose, the Meaning Reconstruction Theory suggests that acceptance and growth comes with integrating loss and rebuilding purpose alongside these changes.

Although the present is different than anticipated, fulfilment is still possible with your current body.

Li-elle Rapaport is a therapist and doctoral candidate in the Department of Psychology, University of Manitoba

This article originally appeared in The Conversation and is republished with permission. 

Slow Broadband Still Hinders Telehealth in Rural Areas

By Crystal Lindell

Unfortunately, the same issue that makes it difficult for some people to access doctors in person can also make it difficult for them to access doctors via telehealth: living in a rural area.

A new study found that nearly 12 million Americans in 41 states lack access to broadband internet sufficient enough to access telehealth appointments — 88% of whom live in rural areas.

Researchers at the Universities of Vermont and Southern Maine say these “broadband deserts” or BBDs have broadband connections slower than 100/20 megabits per second. Their study, published in JAMA, also identified “ambulance deserts” (ADs) and “healthcare deserts” (HCDs) in the United States. 

Nearly 950,000 people live in AD and HCD areas, but have sufficient broadband for telehealth. About 650,000 people live in areas that lacked all three: broadband, ambulance services, and healthcare.

Western states were the most impacted by these issues, and had the highest percentage of rural residents living in BBDs (32%).

Just because you live in a rural area doesn’t make you technologically illiterate. About 95% of rural households have a computing device and 88.5% have a broadband subscription. But their broadband speeds are modest compared to urban areas.

“This cross-sectional study found persistent broadband disparities across 41 states, especially in rural areas of the South and West, where limited internet infrastructure and broadband subscription rates compound challenges in accessing timely medical care,” researchers said.. 

“While broadband availability and subscriptions are prerequisites for telehealth, its presence does not inherently guarantee use. The findings suggest that the potential of telehealth to mitigate gaps in primary, specialty, and emergency care is constrained by inadequate infrastructure and broadband subscription rates.”

Researchers cited two examples of states that have helped close these access gaps, saying they could serve as a model for other states. 

North Dakota now has near-universal fiber connectivity, which was achieved through cooperative broadband initiatives, state leadership, and early federal investments from programs like the American Recovery and Reinvestment Act. 

New Hampshire also leveraged federal funds and local partnerships to rapidly expand high-speed internet to underserved communities.

“These success stories highlight the importance of sustained funding, community-driven networks, and state-level planning that includes assessment of burdensome regulations to enable universal broadband coverage,” researchers said. 

Telehealth services grew by leaps and bounds during the Covid pandemic, when many doctors’ offices were closed and their patients were stuck at home. For a few years, the DEA even allowed telehealth to be used for prescribing opioids and other controlled substances. Those lenient DEA prescribing rules were eventually phased out.

This year Medicare also dropped telehealth coverage for most Americans, but allowed a carve-out for Medicare patients in rural areas to still make telehealth appointments.  

Funding delays and policy debates are currently holding up $21 billion in federal funding for rural internet projects, as states await guidance from the Trump administration on how to the money should be spent.  

More Than Distraction: How Music Relieves Pain 

By Pat Anson

Music won’t cure chronic pain, but there is some evidence that listening to your favorite tunes helps reduce pain levels temporarily. And it’s not just distraction.

The type of music doesn’t seem to matter – whether it’s Mozart or heavy metal – the key seems to be that listeners like what they hear and choose it themselves. Singing or humming along, moving in sync to music, or even playing the air guitar are also good ways to ease pain.

That’s what researchers at Drexel University found when they reviewed 57 clinical studies that evaluated the effects of music on pain.

Like a lot of pain research, many of the studies were small and induced pain in a laboratory by having healthy volunteers briefly dunk their hands in cold water – not the daily pain that comes from arthritis, migraine or an aching back.  

"Researching how music affects pain may sound simple, but it is actually very challenging because of the complexity of music and the complexity of pain," says lead author Joke Bradt, PhD, Professor and Program Director of the PhD in Creative Arts Therapies program at Drexel University.

"In my clinical work, I mostly use active music-making, such as singing, vocal improvisation and playing instruments because I have seen this to be much more effective for chronic pain than merely listening to music.” 

The study findings, recently published in PAIN Reports, suggest that there’s more to music than simple distraction. To be effective, it’s important for the music to be pleasant to the listener to help counteract the unpleasant sensations of pain. Someone who prefers country music or jazz may not get any pain relief listening to heavy metal.  

“Although distraction is often cited as a potential mechanism, current evidence suggests that attentional capture alone is insufficient for hypoalgesia. Unpleasant music or neutral sounds, while engaging attention, typically fail to reduce pain,” researchers found.

“Thus, music does not appear to reduce pain merely through the automatic capture of attention by an auditory stimulus. However, it remains possible that listeners sustain attention toward the music in a more deliberate and controlled manner.”

Active participation also plays a role. The simple act of choosing your own music and humming or singing along helps overcome the passive role that pain often induces. 

 "The findings from our study help explain why music can be an effective, low-risk approach for pain management and how we can maximize its potency," said Bradt.

Little Evidence Back Braces Work for Chronic Low Back Pain

By Pat Anson

Lumbar supports – also known as back braces – are widely used around the world for low back pain. They’re designed to stabilize the lower back and apply gentle compression to the abdomen, giving relief to sore muscles and aching backs.

There’s also little evidence that they work, according to a new Cochrane review by Italian researchers, who looked at the findings of eight randomised controlled trials involving over 500 adults with chronic low back pain. Five of the studies were conducted in low and middle-income countries and three were in high-income countries. 

Researchers found that lumbar supports showed little to no benefit, with the possible exception of a small short-term reduction in pain intensity when used with pain relievers like ibuprofen. The authors were cautious about drawing any further conclusions from the eight trials, and rated the quality of evidence as very low.

“Lumbar supports are widely used in clinical practice despite the fact we know virtually nothing about their effectiveness,” says lead author Chiara Arienti, PhD, an Assistant Professor in the Clinical Epidemiology Research Centre at Humanitas University in Milan. “Drawing from a very thin research base, we still don’t have enough evidence to make broad recommendations for or against their use.”

Arienti and her colleagues say lumbar supports may provide pain relief for three to four weeks when combined with nonsteroidal anti-inflammatory drugs (NSAIDs), but offer little to no benefit when used alone. They were also “very uncertain” about the benefits of lumbar support when combined with exercise and education.

None of the studies tested mobility devices like walking aids or wheelchairs, which could potentially be helpful for older adults and people with disabilities.

Lumbar Supports More Common in Poorer Countries

One interesting finding was the geographic distribution of the research. Most of the trials were conducted in low- and middle-income countries, where lumbar supports are used more routinely. 

In higher income countries, patients are more likely to get exercise therapy, education, and cognitive behavioral therapy for chronic low back pain. Those “active” therapies are less likely to be offered in poorer countries.

"It's striking that most of the research on lumbar supports is coming from areas where active treatments are harder to access," says senior author Stefano Negrini, PhD, a Professor in Physical and Rehabilitation Medicine at the University of Milan. “There’s enough data now showing that active treatments have a clinical effect on low back pain, but these treatments can be very expensive because they require rehabilitation professionals' involvement.”

As the population ages around the world, demand for low-cost treatments is likely to grow. The authors say more research is needed in low to middle-income countries to better understand the value of lumbar supports, particularly for older adults who may not have access to other treatments. 

“We have to ask ourselves whether we are looking at this problem only through the lens of the Global North, and whether that is the right perspective. These devices may play a different and important role in contexts where the alternative simply isn't available," Negrini said.

Chronic lower back pain is the leading cause of disability worldwide. Over 72 million U.S. adults suffer from it, according to a 2022 Harris Poll. About a third of those surveyed rated their pain as severe and nearly half said they experienced chronic back pain for at least five years. 

Although lower back pain is quite common, there is little consensus on how to treat it. Most of the clinical trial evidence is considered low or very low quality, a persistent problem.in many medical guidelines dealing with pain. 

How Messaging in Patient Portals Impacts Care

By Crystal Lindell

What you write in texts and messages to your doctor can impact the quality of care that you receive, according to a new study published in JAMA. 

Researchers at Harvard and Columbia University analyzed over 3.5 million patient messages sent by over half a million patients through patient portals like MyChart. They wanted to see how a patient’s race, education and other demographics might influence how doctors respond to their messages.

Researchers found “substantial differences” in how providers responded to historically marginalized groups, such as Blacks and Hispanics, but found that a patient’s writing style had more impact on how care teams responded. If they were polite and positive, a patient was more likely to get a response.

“Writing style was a more important factor. Seemingly minor differences among messages, such as whether the opening included the target clinician’s name, were associated with significantly different response rates,” researchers reported.

For example, when patient messages included a clinician’s last name in the opening line, such as “Dear Dr. Smith,” those messages had a 38.7% response rate.

But when a message had no greeting at all -- no salutation or even a simple “hello” – those messages had just a 25.7% response rate.

Providers were also more likely to respond to messages that had a positive sentiment; used expressive punctuation such as question and exclamation marks; and higher word counts. 

To illustrate what they found, researchers asked ChatpGPT to write two messages from the perspective of a patient with respiratory symptoms. 

One message was polite and positive – written in a way to get a high response rate: 

"Dear Dr. Liu, 

I hope you're doing well! I wanted to reach out because I've been experiencing some new respiratory symptoms that I'm a little concerned about and would really appreciate your perspective. Over the past two days, I've developed a dry, persistent cough along with some chest tightness and mild shortness of breath -- especially when walking or going up stairs. 

I haven't had a fever, but the symptoms are definitely noticeable and seem to be getting a bit worse, which is making me wonder if there could be something more going on? I know you've helped me manage my asthma in the past, could this be a flare-up or something else entirely?? 

Thanks so much again for all you do! I really appreciate your time and guidance. 

Warmly, 

Peter Parker

The other patient message was short and blunt – written in a way that researchers thought would get a poor response rate: 

"I've had a cough and congestion for a few days now, and it's been pretty uncomfortable. Still no fever, but it's been dragging on and making it harder to get through the day."

See the difference? The more polite and positive message, though much longer, is more likely to get a response. Writing style was a possible explanation for about half of the disparities that researchers found in response rates. 

“In many message triage systems, nurses and medical assistants must quickly assess messages — often with little context — and make snap judgments on their urgency, complexity, and need for escalation. Given these constraints, it is not surprising that writing style factors might influence the triage process,” researchers said.

Patient portals provide an easy and convenient way for patients to send messages to their physicians, but put an extra burden on doctors to respond. Some do and some don’t – depending on the patient.

So the next time you write a text or message to your doctor, make an effort to be polite and positive. Use words like “please” and “thanks.” Simply being polite can have some surprisingly positive outcomes.  

Is Dry Needling Effective for Muscle Pain?

By The Conversation

Physiotherapists, chiropractors and osteopaths commonly use dry needling to treat neck, shoulder, back and other types of muscle pain.

It involves inserting thin needles into sensitive parts of a person’s muscle, often termed “myofascial trigger points”. The needles remain in the muscle for a few minutes and can be gently moved to create a twitch response in the muscle.

This therapy is thought to relax the muscle, reduce inflammation, promote healing and reduce pain. But does it actually work? And what are the risks?

Similar to Acupuncture

Dry needling is similar to acupuncture: they’re both applied to reduce pain.

Both treatments use solid, single use needles. They’re commonly 30–75mm long and 0.2–0.3mm thick, although longer needles may be used for deeper muscles. Unlike injection needles, they aren’t hollow and don’t inject medication.

A key difference is how the needle locations are chosen. Traditional acupuncture selects points based on symptoms and Chinese medicine concepts, including balancing qi as it flows through pathways called meridians. Dry needling is applied directly to tissue that’s thought to be the cause of symptoms.

Gaining Popularity

People seeing a physiotherapist for aches and pains are increasingly being offered dry needling. A 2023 survey of 203 Australian physiotherapists found 64% use dry needling on their patients.

The surveyed physiotherapists believed dry needling was an effective pain reliever and thought it was particularly effective alongside treatments such as exercise or manual therapy (which encompasses massage and manipulation or “joint cracking”).

In Australia, registered physiotherapists, chiropractors and osteopaths meet the safety standards required to use dry needling if they have completed training. The training usually involves a short (weekend) course.

Does Dry Needling Work?

Several research studies have collated the available evidence on dry needling. Most conclude it provides short-term pain relief for conditions such as neck pain, shoulder pain and low back pain, but is no better than other common treatments such as exercise.

Clinical practice guidelines are what health-care providers should use to dictate which treatments to provide and not provide. However, few clinical practice guidelines recommend dry needling.

There are two main reasons why.

Nearly all studies investigating the benefits of dry needling have serious concerns about how they’re conducted. This includes not being able to determine whether the benefits of dry needling are genuine or simply reflect placebo effects – when your health improves after receiving a fake treatment.

So it remains unclear whether dry needling provides benefits beyond a placebo.

Another reason is the potential risks of dry needling.

What Are the Risks?

Inserting thin and extremely sharp needles into the body requires an excellent understanding of anatomy.

Health-care providers need to be extremely careful to avoid major arteries, veins and nerves when dry needling around the neck and avoid puncturing the lungs when dry needling around the “traps” (trapezius muscles) and torso.

There have been cases of providers puncturing their patients’ lungs during dry needling, prompting a medical emergency.

In June, it was revealed that a Western Australian physiotherapist had her registration suspended for three months after puncturing a patient’s lungs, causing bilateral pneumothoraxes – the collapse of both lungs.

In November, Pittsburgh Steelers NFL player TJ Watts had to undergo emergency surgery after a similar injury caused a partial lung collapse.

Despite the risks, half of the studies on dry needling don’t mention if any adverse events occurred.

The studies that do report risks suggest serious risks such as a collapsed lung, infection or broken needle that gets stuck in a person’s body are very rare.

But we don’t know exactly how rare this is. Data from a large study on acupuncture suggests these adverse events occur in approximately one in 100,000 patients. But it’s unclear if the risk is the same for dry needling.

Less-serious side effects such as minor bleeding, bruising, soreness at the needling site or temporary symptom aggravation seem to be common.

Some factors also increase some risks, such as taking blood thinning medication or having an immune disorder.

Talk to Your Provider

Because the evidence on dry needling is uncertain and risks have not been adequately reported in the research, it’s important to discuss the benefits, risks and practicalities of dry needling with your health-care provider.

If your goal is short-term pain relief, consider asking your provider if there are other options that could provide similar relief.

If you have a fear of needles or have fainted when undergoing a needling procedure previously, such as a blood test, then dry needling might not be the best treatment for you.

Before undergoing dry needling, it’s important you have had a chance to ask questions and been given sufficient information about the treatment before providing informed consent.

Questions you might ask your health-care provider include:

  1. What are my treatment options?

  2. What are the potential benefits and risks of these options?

  3. How likely is it that those benefits and risks could happen to me?

Although other treatments are as effective or more effective with fewer potential side effects, dry needling might be useful for some people. But a discussion of risks and benefits should always be transparent and ongoing.

Luke Jenkins, PhD, is Lecturer in Physiotherapy at Western Sydney University.

Giovanni Ferreira, PhD, is a Research Fellow, Institute of Musculoskeletal Health, at the University of Sydney.

Joshua Zadro, PhD, is an Associate Professor of Physiotherapy at the University of Sydney.

Peter Stubbs, PhD, is an Associate Professor of Physiotherapy at the University of Technology Sydney.

This article originally appeared in The Conversation and is republished with permission.  

Swimming Reduces Disability From Chronic Low Back Pain

By Mark Hancock and Deborah Wareham

As we age, low back pain becomes more common. Between the ages 20 and 59, persistent low back pain (lasting more than three months) affects nearly one in five.

While you may be tempted to reach for heat packs, medication or a massage, new evidence suggests that the common advice to go for a swim is much more effective.

Until recently, there was no research to back up this advice. Our new trial shows for the first time that swimming can improve low back pain.

What We Did

We recruited 76 adults aged 26 to 74 who experienced persistent and bothersome low back pain for more than three months. They needed to be able to swim 25 meters (82 feet) independently, but didn’t swim regularly.

The participants were randomly allocated to receive either a swimming and education program (the intervention group) or education only (the control group).

The intervention involved an eight-week individualised swimming program, supported by four telehealth sessions with a physiotherapist, and free access to a local indoor or outdoor swimming pool.

The amount of swimming was tailored to each participant’s ability and fitness level, with the goal of completing three 30–45 minute swimming sessions per week by the end of the program. Participants were encouraged to continue swimming after the program completed.

The education, provided by a physiotherapist, aimed to help them better understand their pain, reduce the fear associated with movement and exercise, and increase confidence to manage their back pain.

While many people with back pain believe they should avoid activity to protect their back, a large body of evidence shows remaining active is better.

Participants in the education-only (control) group had one to two sessions with a physiotherapist to cover the same key messages about back pain, but otherwise continued their usual treatment and activity.

What Did We Find?

Participants in the swimming group reported improved function, less pain and more confidence to manage future back pain.

Their disability reduced by more than 50% at the end of the eight-week program. This could mean that a person improved their ability to do daily activities such as standing from a chair, walking or sleeping.

The swimming group’s improvements were 30% greater than those who received education only (control) group.

Participants told us swimming appealed to them because it was low-impact, it reduced weight-bearing and strain, and it enabled them to exercise more confidently and with less pain. They also reported additional health benefits, including better mood.

Swimming can be used as a way for people with back pain to start exercising and break the cycle of pain and limited activity.

At the end of the eight-week program, some people kept swimming, others swapped to another form of exercise and some stopped exercising.

Although most participants reported enjoyed swimming, some found accessing a pool and the time required a barrier to keep going in the longer term.

Twelve months after starting the program, there were still benefits for the swimming group for disability, function and confidence. But the difference between groups became smaller over time.

Our study’s sample size was relatively small, so these findings need to be confirmed in future, larger studies.

Further trials are also needed to test whether the results still hold for people with more severe or disabling back pain.

Finally, the volunteers in our study knew we were investigating swimming and had positive expectations of swimming before starting. This is a limitation that could affect the findings.

Swimming vs Other Exercises

A range of different exercises – including Pilates, functional exercises (a type of strength training that helps you perform daily activities) and structured walking – have been shown to be beneficial for treating disability and preventing low back pain recurrences.

While we didn’t compare swimming to another type of exercise, the benefits we identified were as large or larger than previously reported for other exercises.

People with chronic low back pain can now consider swimming as an evidence-based exercise option and be more confident in choosing it as part of their long-term management.

But if you find it a hassle to get to a pool, or don’t like swimming, it may help get your back pain under control before moving to a type of exercise you prefer or can more easily access.

Mark Hancock, PhD, is a Professor of Physiotherapy, Faculty of Medicine and Health Science, at Macquarie University in Australia. 

Deborah Wareham, PhD, is a Research Fellow at the Spinal Pain Research Centre at Macquarie University.

This article originally appeared in The Conversation and is republished with permission.    

Palmitoylethanolamide (PEA): A Natural Treatment for Intractable Pain

By Dr. Forest Tennant and Ingrid Hollis 

Palmitoylethanolamide (PEA) is a naturally occurring biochemical produced by the body for pain and inflammation control. It is also available as an over-the-counter dietary supplement. 

This article is presented with our belief that essentially every person with intractable pain should try a PEA supplement in a therapeutic trial.  Several companies market PEA supplements and researchers have determined effective dosages. 

PEA is the only medicinal that simultaneously fights inflammation at the site of an injury, as well as neuroinflammation in the central nervous system (CNS).  It helps heal damaged glial cells that are responsible for intractable or constant pain. 

About two dozen double-blind clinical studies have shown that PEA is more than just a placebo. German researchers say PEA is an effective and well-tolerated treatment for hundreds of patients with chronic pain.    

Our experience is not as extensive, but we have found that about 80% of patients experience good results if PEA is used for four to six weeks, providing relief for both chronic and intractable pain.  In most patients, PEA progressively wears down baseline pain. 

Starting dosage is 600 to 1200 mg twice a day.  This dosage can be increased if needed.  

Some PEA products contain luteolin, a polyphenol found in many fruits, vegetables and herbs that has anti-oxidant and anti-inflammatory properties. This is excellent as luteolin boosts the effectiveness of PEA, and also helps prevent the reactivation of the Epstein-Barr virus. 

One can simply add PEA to their current pain relief program.  Opioids and other pain medications need not be stopped. 

No serious side effects have been reported from taking PEA. As a natural biochemical, it is quite safe to take.  

If you have chronic or intractable pain, try a 1-to-2-month therapeutic trial of PEA. You have much to gain and nothing to lose. 

Forest Tennant, MD, DrPH, is retired from clinical practice but continues his research on the treatment of intractable pain and arachnoiditis. Readers interested in learning more about his research should visit the Tennant Foundation’s website, Arachnoiditis Hope. You can subscribe to its bulletins here.

Ingrid Hollis is a person in pain, patient advocate, and advisor to the Tennant Foundation.

The Tennant Foundation gives financial support to Pain News Network and sponsors PNN’s Patient Resources section. 

Melatonin Can Help Reduce Chronic Pain

By Pat Anson

Many chronic pain sufferers know how beneficial a good night’s sleep can be. Restorative sleep reduces pain levels, along with fatigue, anxiety and stress.

A new study in Australia suggests that melatonin not only helps with sleep, but is just as effective at reducing chronic musculoskeletal pain as non-steroidal anti-inflammatory drugs (NSAIDs). 

The study, published in the journal PAIN, looked at health data for over 2,000 patients in 23 controlled trials who took melatonin supplements. Participants included people with low back pain, osteoarthritis and fibromyalgia, as well as those recovering from joint replacements and spinal surgeries. 

“For many patients, pain doesn’t exist in isolation and is closely tied to poor sleep,” said lead author and PhD student Kangchao Wu in the Musculoskeletal Research Hub at the University of Sydney. “Melatonin appears to target both, which makes it particularly useful for people managing chronic pain.

Using a zero to 100 pain scale, researchers say melatonin modestly reduced musculoskeletal pain by about nine points, with the most rigorous studies showing pain levels dropping nearly 10 points, a level similar to those of NSAIDs. Melatonin was not as effective in reducing post-operative pain.

Notably, researchers did not find evidence of a dose-response relationship, meaning no single “best” dose of melatonin can be recommended. 

“The level of pain relief we observed is comparable to some conventional treatments, but this does not mean melatonin should replace them,” Wu said. “Rather, it may offer a safer additional option within a broader pain management plan.”

Melatonin is a natural hormone produced by the pineal gland in the brain. During the day the pineal gland is inactive, but at night it begins to produce melatonin and helps us sleep.

Melatonin supplements are widely promoted as sleep aids. However, their role in reducing inflammation – a major contributor to chronic pain – may be just as important. Melatonin has antioxidant and anti-inflammatory properties, which may reduce the central sensitization and inflammation underlying chronic pain.

In Europe and Australia, melatonin requires a prescription, while in the United States melatonin supplements can be purchased over-the-counter.

“Melatonin is already in people’s homes, it’s inexpensive, and we know it’s safe,” says Wu. “What’s exciting is that melatonin may also help manage chronic pain, opening the door to reducing reliance on medications that come with more risks.”

Melatonin is generally well tolerated, with mild, short-term side effects such as nausea, dizziness and headaches. Melatonin is considered safe for short-term use of less than three months. 

A recent study found that adults with insomnia who used melatonin for at least a year were more likely to be diagnosed with heart failure, be hospitalized, or die from any cause. The study did not establish a cause-and-effect relationship, meaning health conditions raising the risk may have already been present.
