
Should AI Be Used to Prompt People in Pain to Exercise?

By Crystal Lindell

We all know that being too sedentary contributes to poor health. It might even make your pain worse. But many of us still spend way too much time sitting in one place watching TV, scrolling on our phones, or working at a computer.   

“Individuals with certain chronic pain disorders face a paradox: they are at increased risk for sedentary behavior due to pain-related interference, even though significant gains in symptom relief and health benefits from increasing their PA (physical activity) for symptom management have been demonstrated,” says Ipek Ensari, PhD, who studies artificial intelligence (AI) and human health. 

Ensari and her colleagues at the Icahn School of Medicine at Mount Sinai wondered if wearable devices could be used to help women with chronic pelvic pain stand up and move around more. 

Their study, recently published in the journal Women’s Health, wanted to see if AI could predict when patients would have prolonged periods of inactivity. 

They recruited 134 women with chronic pelvic pain, primarily from endometriosis, along with 61 healthy women for a control group. Participants wore Fitbit devices for up to 90 days, generating minute-by-minute information about their physical activity, heart rate, steps, and sleep patterns.

"Our goal was to determine whether everyday wearable devices could serve as an early-warning system for prolonged sitting in women living with chronic pelvic pain," Ensari explained in a news release. 

"Rather than offering generic advice after the fact, we wanted to determine whether we could anticipate these moments and support people with simple, well-timed prompts that fit naturally into their daily lives."

The research team gathered data from each participant and developed personalized forecasting models to predict their activity levels one hour ahead of time. The goal was to identify 15-minute periods when a participant could stand up and move around, which the researchers called an “exercise snack.” 

Those short activity breaks may be more realistic and achievable than longer exercise periods, especially for people with chronic pain. The work also challenged the assumption that AI focused on health needs to be complex. Relatively simple AI models forecast prolonged periods of sitting just as well as complex ones.   

"We were surprised by how well the simplest models performed," said lead author Jannes Jegminat, PhD, a former postdoctoral research fellow at the Icahn School of Medicine. "More complex AI is not always better. Lightweight, interpretable models can accurately forecast sedentary behavior while being practical enough to run directly on a person's own device, which also helps protect privacy." 

Unfortunately, the research did not include any further investigation into whether or not participants would actually get up for a walk when prompted. And there seems to have been no consultation with pain patients on whether this technology is something they’d want and use.

The researchers admit that further study is needed to see if the AI prompts could actually help patients.

"This study suggests that predicting prolonged sitting is feasible, even if the individual has chronic conditions that might impact their daily routine," said Ensari. "The next step is determining whether delivering personalized movement prompts based on those predictions actually helps reduce sedentary time, improves symptoms, and enhances quality of life. Those questions will require prospective clinical trials."

It’s unclear how the technology would be applied to periods when someone needs to be sedentary, such as when they are working, eating, watching a favorite show, or in too much pain to move. 

The last thing I want to see on my AI watch as I’m driving late to work is a notification telling me to go for a walk instead.  

It’s becoming clear that anything and everything related to artificial intelligence is the new trendy topic for research, and it’s likely the topic is now also yielding better funding opportunities. But as researchers continue to study the ways AI can help us medically, they would do well to remember to ask patients for their input as well.

My Cats Help Me Cope with Chronic Pain

By Crystal Lindell

It is ironic that I was initially opposed to getting a cat because I have chronic pain.

I hate getting up early. I hate having to do anything right when I wake up. And I have no money.  

Cats wake you up at 5 am, expect to be fed immediately, and keeping them alive is expensive.

But when the mother of my fiancé Chris moved into senior housing, she was only allowed to take one of her two cats with her.

Thus, her long-haired tortoiseshell cat – affectionately named Princess Diana – had nowhere to go but to our house.

Although I was initially reluctant, Princess D quickly won me over when, on her first visit, she ran over to me while I was sitting in a rocking chair. She stared up at me with the eyes of a cat looking for love, and jumped up into my lap.  

I was hooked.

We became a one cat household.

Eventually, Princess D’s former sister Basil was also looking for a home, after Chris’ mom was no longer able to care for her either.

CRYSTAL WITH PRINCESS DIANA

Basil, a beautiful long-haired black cat, came with a pre-written warning for the vet, and lots of war stories. She was a scratcher. And a biter. If we hadn’t taken her, they were going to put her down.

Over the years, in the comfort and predictability of our home, Basil has softened. But just last week, she bit my arm because she got confused in the middle of the night.

We love her regardless.

After Basil came to live with us, we found our orange boy Goose and our brown tabby Goldie Hawn, outside. 

And when we moved in with my relatives, two gray-haired cats, Gracie and Cinnamon, joined our crew.

Yes, that brings the total to six cats. Yes, I know that puts me into crazy cat lady territory. But the thing about being a crazy cat lady is that I love them all too much to care what you think.

Just as I feared, they do all wake us up at 5 am, asking for food. And it does indeed feel like I’m pulling myself out of cement to get out of bed, just so that I can open a can of Friskies for them at dawn.

Truth be told though, having a reason – actually six reasons – to get out of bed every morning goes a long way when you’re dealing with pain that never ends. They give me purpose, and in return, I give them treats.

Having six cats also means that at least one of them is always willing to nap with me whenever I’m having a bad pain day. And naps covered in cats are healing. 

I confess, we do spend a lot of our money on our cats, especially after Princess Diana developed diabetes and almost died. We buy $140 vials of insulin every other month to keep her alive.

But she keeps me alive by giving me a reason to live, so really it all evens out.

In the end, our six cats give my life meaning, relieve stress, take my mind off my pain, and fill our home with love. All of those things go a very long way toward helping me cope with chronic pain.

In fact, there’s even data to back this up.  

In 2019, a National Poll on Healthy Aging conducted by AARP and the University of Michigan found that pets can offer their owners a wide range of health benefits.

The people surveyed said their pets helped them enjoy life (88%), made them feel loved (86%), helped reduce stress (79%), kept them physically active (64%) and helped them cope with physical and emotional symptoms (60%), such as taking their mind off pain (34%).

For those who said their health was fair or poor, pet ownership offers the most benefits. More than 70% of older adults said their pet helps them cope with life’s challenges, and nearly half (46%) said their pets help distract them from pain.

I used to think that having chronic pain was why I could never care for a pet. But I’ve come to understand that caring for a pet is one of those things that gives more than it takes. It’s because of my chronic pain, that having a pet – or six of them – is so vital to my well-being.

Less Is More: It Doesn’t Take Much Exercise to Reduce Pain

By Pat Anson

It won’t cure you or make your pain go away, but moderate levels of exercise could give you some relief from acute and chronic pain, according to a new study by Australian researchers.

In a systematic review of 157 clinical trials, a research team at Adelaide University found that less than two hours of exercise a week could reduce pain by about 1.1 points on the zero-to-ten pain scale. In fact, exercise of low intensity and short duration appears to be more beneficial than longer, intense workouts.

“Our study found that exercise was associated with substantial reductions in acute and chronic pain across all forms of exercise – whether that be via aerobic or resistance exercise, or through gentler movement such as yoga, Pilates or tai chi,” lead author Ben Singh, PhD, a Research Fellow at Adelaide’s School of Allied Health and Human Performance, said in a press release.

“Importantly, we found that more exercise wasn’t necessarily better. In fact, shorter-duration and lower-intensity programs showed greater reductions in pain, suggesting people may not need to exercise harder or for longer to experience meaningful benefits.”

The study findings, published in the journal PAIN Reports, show the most significant reductions were for pain caused by these conditions:

  • Axial spondylarthritis

  • Cancer

  • Musculoskeletal conditions

  • Fibromyalgia

  • Hip replacement

  • Low back pain

  • Migraine and headache

  • Neck pain 

  • Osteoarthritis

  • Idiopathic pain in older adults

  • Osteoporosis

  • Menopause

  • Pregnancy-related pain

  • Primary dysmenorrhea

  • Rheumatoid arthritis 

Low intensity workouts from tai chi, yoga and Pilates were beneficial, but the form of exercise that produced the largest reduction in pain was a bit of a surprise: Dancing.

That finding, however, is based on a single study of dancing by fibromyalgia patients and should be taken with caution. “Although dance-based interventions may offer promise for this population,” researchers say further studies are needed to prove the effect.

There are four key reasons why exercise has an analgesic effect.

First, exercise stimulates the release of endogenous hormones (endorphins), which act as natural painkillers and increase pain tolerance.

Second, exercise enhances the production of neurotransmitters such as serotonin and norepinephrine, which play crucial roles in mood and pain modulation.

Third, exercise reduces systemic inflammation, a common driver of chronic pain, by modulating immune system function.

Finally, exercise activates the body’s endocannabinoid system, which helps to modulate pain perception, mood, and inflammation.

“When we exercise, our body releases chemicals including endorphins and serotonin that can help reduce how strongly we feel pain and increase our pain tolerance,” Singh explained. “Additionally, it helps calm inflammation and change the way our brain responds to pain, while also improving mood.

“These effects help explain why exercise can be such a powerful tool for pain management. Yet despite the evidence, it isn’t used as routinely as it could be and is rarely prescribed with the same precision as medication.”

The idea that exercising less than 2 hours a week is more effective runs counter to many current exercise guidelines, which recommend 150 minutes or more per week. That amount can feel unattainable for many people with chronic pain. Shorter, less intense physical activity is more realistic and may help people overcome their resistance to exercise. 

“These findings support starting with manageable, lower-dose (exercise) programs to build confidence, promote adherence, and reduce fear of symptom flare-ups, key barriers for people with chronic pain,” researchers concluded. 

“Exercise should not be considered a universal solution or expected to eliminate pain entirely. Its efficacy will depend on individual factors such as the underlying pain condition, level of physical function, and adherence.” 

Mourning the Loss of a Healthy Body

By  Li-elle Rapaport 

Body changes can raise disturbing feelings, such as looking in a mirror and seeing a reflection that may feel spiritually empty, unproductive, ugly or weak.

Unpleasant sensations such as pain, pins and needles, soreness coursing through limbs and an inexplicable fog filling the head are a reminder that this body is not the same you anymore, prompting us to wish there was a way to get back there. It may feel impossible to live well unless you do.

This is the disillusionment that most of the population will face at some point in life, through aging, chronic pain or invisible illness (a disease or health problem that cannot be externally seen, including autoimmune diseases, chronic pain and fatigue, and recently, long COVID).

Recent global estimates suggest one in five people are currently experiencing chronic pain. The most prevalent chronic pain reported by adults ages 75 and over includes low back pain and migraine, while tension-type headaches are more often experienced by younger adults. Chronic illness (diabetes, heart disease and other mid-to-late-life diagnoses) affects about three-quarters of the world population.

Despite how common chronic illness is worldwide, the nuances of navigating a changing body are not often discussed. It’s time for an honest, evidence-based conversation about what it means to navigate chronic pain and illness, aging and transforming identity post-diagnosis, and how to grieve this loss and maintain meaning through these changes.

Why It Matters

Research suggest that those with internalized stigma of chronic illness are more preoccupied with how their illness detracts from their view of themselves, and also have a greater tendency to overlook positive aspects of life with a chronic illness.

Psychologists have observed how preoccupation with illness or pain is often accompanied by other grief behaviours. A 2025 study explored how Danish chronic illness patients navigated loss and growth. The study found that many with chronic illness find themselves mourning the life that they thought they would have, often leading to loss of motivation and joy in everyday life.

The perception of losing the life they had once envisioned is often accompanied by a focus on getting back to the “before illness” version of themselves as people struggle to accept how their body has changed, perhaps in how it looks but definitely in how it feels.

These changes and associated feelings of loss often permeate a person’s sense of identity, as well as their perceived roles within social relationships. Many report a fear of burdening others, especially loved ones, often describing feelings of guilt that “others have it worse than I do.” This is where internalized stigma festers.

Some people have also described feelings of anger, isolation, shame and exhaustion accompanying sadness. Meanwhile, others have expressed frustration over a gradual loss rather than a “clean break,” accompanied by the inability to find closure.

Making Sense of Grief

First, it’s important to understand why accepting this continuous loss feels so impossible. Theories of control in psychology state that humans desire control or the ability to achieve a desired outcome according to our own standards.

When that ability is seen as stripped away, people are more likely to experience negative mental health symptoms, like anxiety, depression and even grief. Specifically, feelings of diminished perceived control (subjective belief about our ability to achieve desired outcomes) occur when we face continuous roadblocks to living our desired life because of chronic illness.

One of the major consequences of loss and major life change is that it can disrupt meaning and challenge identity, purpose and assumptions about the future. At a time when people feel there is little they can control, psychologist Robert Neimeyer’s Meaning Reconstruction Theory poses the questions: “How do I move forward?” and “What matters most?”

While the original theory was proposed as an approach to coping with the loss of a loved one, the process is somewhat similar to grieving the close ally that is your body. This theory approaches grief by making sense of the loss and finding ways to rebuild a sense of purpose in a changed life (and body).

To answer relevant questions about how to move forward with chronic illness, two ongoing approaches are needed: integrating the loss and recentring purpose and meaning.

Integrating the loss may look like processing significant bodily losses in therapy, finding trusted loved ones to talk about the loss with and focusing on being realistic about your current body without judgment.

Second, recentring purpose during this major life change involves understanding your why: why is this loss so significant to you, why does it hurt? Maybe it’s because you love hiking in the mountains and a new diagnosis with arthritis feels like the end of this joy. Part of rebuilding meaning is finding new approaches to fulfilling this purpose — perhaps hiking may look different, but nature can be accessed and loved with chronic illness present.

Rebuilding meaning might also look like making meaning from this loss: What has this change taught you about yourself, about the impact you can make? Approaching present and future with this perspective helps process grief in a more protective way.

Living with chronic pain, illness and the changes that come with aging often involves grieving physical loss, but also shifts in purpose, relationships, identity and future plans. While these changes challenge our perceived control and purpose, the Meaning Reconstruction Theory suggests that acceptance and growth comes with integrating loss and rebuilding purpose alongside these changes.

Although the present is different than anticipated, fulfilment is still possible with your current body.

Li-elle Rapaport is a therapist and doctoral candidate in the Department of Psychology, University of Manitoba

This article originally appeared in The Conversation and is republished with permission. 

Slow Broadband Still Hinders Telehealth in Rural Areas

By Crystal Lindell

Unfortunately, the same issue that makes it difficult for some people to access doctors in person can also make it difficult for them to access doctors via telehealth: living in a rural area.

A new study found that nearly 12 million Americans in 41 states lack access to broadband internet sufficient enough to access telehealth appointments — 88% of whom live in rural areas.

Researchers at the Universities of Vermont and Southern Maine say these “broadband deserts” or BBDs have broadband connections slower than 100/20 megabits per second. Their study, published in JAMA, also identified “ambulance deserts” (ADs) and “healthcare deserts” (HCDs) in the United States. 

Nearly 950,000 people live in AD and HCD areas, but have sufficient broadband for telehealth. About 650,000 people live in areas that lacked all three: broadband, ambulance services, and healthcare.

Western states were the most impacted by these issues, and had the highest percentage of rural residents living in BBDs (32%).

Just because you live in a rural area doesn’t make you technologically illiterate. About 95% of rural households have a computing device and 88.5% have a broadband subscription. But their broadband speeds are modest compared to urban areas.

“This cross-sectional study found persistent broadband disparities across 41 states, especially in rural areas of the South and West, where limited internet infrastructure and broadband subscription rates compound challenges in accessing timely medical care,” researchers said.. 

“While broadband availability and subscriptions are prerequisites for telehealth, its presence does not inherently guarantee use. The findings suggest that the potential of telehealth to mitigate gaps in primary, specialty, and emergency care is constrained by inadequate infrastructure and broadband subscription rates.”

Researchers cited two examples of states that have helped close these access gaps, saying they could serve as a model for other states. 

North Dakota now has near-universal fiber connectivity, which was achieved through cooperative broadband initiatives, state leadership, and early federal investments from programs like the American Recovery and Reinvestment Act. 

New Hampshire also leveraged federal funds and local partnerships to rapidly expand high-speed internet to underserved communities.

“These success stories highlight the importance of sustained funding, community-driven networks, and state-level planning that includes assessment of burdensome regulations to enable universal broadband coverage,” researchers said. 

Telehealth services grew by leaps and bounds during the Covid pandemic, when many doctors’ offices were closed and their patients were stuck at home. For a few years, the DEA even allowed telehealth to be used for prescribing opioids and other controlled substances. Those lenient DEA prescribing rules were eventually phased out.

This year Medicare also dropped telehealth coverage for most Americans, but allowed a carve-out for Medicare patients in rural areas to still make telehealth appointments.  

Funding delays and policy debates are currently holding up $21 billion in federal funding for rural internet projects, as states await guidance from the Trump administration on how to the money should be spent.  

More Than Distraction: How Music Relieves Pain 

By Pat Anson

Music won’t cure chronic pain, but there is some evidence that listening to your favorite tunes helps reduce pain levels temporarily. And it’s not just distraction.

The type of music doesn’t seem to matter – whether it’s Mozart or heavy metal – the key seems to be that listeners like what they hear and choose it themselves. Singing or humming along, moving in sync to music, or even playing the air guitar are also good ways to ease pain.

That’s what researchers at Drexel University found when they reviewed 57 clinical studies that evaluated the effects of music on pain.

Like a lot of pain research, many of the studies were small and induced pain in a laboratory by having healthy volunteers briefly dunk their hands in cold water – not the daily pain that comes from arthritis, migraine or an aching back.  

"Researching how music affects pain may sound simple, but it is actually very challenging because of the complexity of music and the complexity of pain," says lead author Joke Bradt, PhD, Professor and Program Director of the PhD in Creative Arts Therapies program at Drexel University.

"In my clinical work, I mostly use active music-making, such as singing, vocal improvisation and playing instruments because I have seen this to be much more effective for chronic pain than merely listening to music.” 

The study findings, recently published in PAIN Reports, suggest that there’s more to music than simple distraction. To be effective, it’s important for the music to be pleasant to the listener to help counteract the unpleasant sensations of pain. Someone who prefers country music or jazz may not get any pain relief listening to heavy metal.  

“Although distraction is often cited as a potential mechanism, current evidence suggests that attentional capture alone is insufficient for hypoalgesia. Unpleasant music or neutral sounds, while engaging attention, typically fail to reduce pain,” researchers found.

“Thus, music does not appear to reduce pain merely through the automatic capture of attention by an auditory stimulus. However, it remains possible that listeners sustain attention toward the music in a more deliberate and controlled manner.”

Active participation also plays a role. The simple act of choosing your own music and humming or singing along helps overcome the passive role that pain often induces. 

 "The findings from our study help explain why music can be an effective, low-risk approach for pain management and how we can maximize its potency," said Bradt.

Little Evidence Back Braces Work for Chronic Low Back Pain

By Pat Anson

Lumbar supports – also known as back braces – are widely used around the world for low back pain. They’re designed to stabilize the lower back and apply gentle compression to the abdomen, giving relief to sore muscles and aching backs.

There’s also little evidence that they work, according to a new Cochrane review by Italian researchers, who looked at the findings of eight randomised controlled trials involving over 500 adults with chronic low back pain. Five of the studies were conducted in low and middle-income countries and three were in high-income countries. 

Researchers found that lumbar supports showed little to no benefit, with the possible exception of a small short-term reduction in pain intensity when used with pain relievers like ibuprofen. The authors were cautious about drawing any further conclusions from the eight trials, and rated the quality of evidence as very low.

“Lumbar supports are widely used in clinical practice despite the fact we know virtually nothing about their effectiveness,” says lead author Chiara Arienti, PhD, an Assistant Professor in the Clinical Epidemiology Research Centre at Humanitas University in Milan. “Drawing from a very thin research base, we still don’t have enough evidence to make broad recommendations for or against their use.”

Arienti and her colleagues say lumbar supports may provide pain relief for three to four weeks when combined with nonsteroidal anti-inflammatory drugs (NSAIDs), but offer little to no benefit when used alone. They were also “very uncertain” about the benefits of lumbar support when combined with exercise and education.

None of the studies tested mobility devices like walking aids or wheelchairs, which could potentially be helpful for older adults and people with disabilities.

Lumbar Supports More Common in Poorer Countries

One interesting finding was the geographic distribution of the research. Most of the trials were conducted in low- and middle-income countries, where lumbar supports are used more routinely. 

In higher income countries, patients are more likely to get exercise therapy, education, and cognitive behavioral therapy for chronic low back pain. Those “active” therapies are less likely to be offered in poorer countries.

"It's striking that most of the research on lumbar supports is coming from areas where active treatments are harder to access," says senior author Stefano Negrini, PhD, a Professor in Physical and Rehabilitation Medicine at the University of Milan. “There’s enough data now showing that active treatments have a clinical effect on low back pain, but these treatments can be very expensive because they require rehabilitation professionals' involvement.”

As the population ages around the world, demand for low-cost treatments is likely to grow. The authors say more research is needed in low to middle-income countries to better understand the value of lumbar supports, particularly for older adults who may not have access to other treatments. 

“We have to ask ourselves whether we are looking at this problem only through the lens of the Global North, and whether that is the right perspective. These devices may play a different and important role in contexts where the alternative simply isn't available," Negrini said.

Chronic lower back pain is the leading cause of disability worldwide. Over 72 million U.S. adults suffer from it, according to a 2022 Harris Poll. About a third of those surveyed rated their pain as severe and nearly half said they experienced chronic back pain for at least five years. 

Although lower back pain is quite common, there is little consensus on how to treat it. Most of the clinical trial evidence is considered low or very low quality, a persistent problem.in many medical guidelines dealing with pain. 

How Messaging in Patient Portals Impacts Care

By Crystal Lindell

What you write in texts and messages to your doctor can impact the quality of care that you receive, according to a new study published in JAMA. 

Researchers at Harvard and Columbia University analyzed over 3.5 million patient messages sent by over half a million patients through patient portals like MyChart. They wanted to see how a patient’s race, education and other demographics might influence how doctors respond to their messages.

Researchers found “substantial differences” in how providers responded to historically marginalized groups, such as Blacks and Hispanics, but found that a patient’s writing style had more impact on how care teams responded. If they were polite and positive, a patient was more likely to get a response.

“Writing style was a more important factor. Seemingly minor differences among messages, such as whether the opening included the target clinician’s name, were associated with significantly different response rates,” researchers reported.

For example, when patient messages included a clinician’s last name in the opening line, such as “Dear Dr. Smith,” those messages had a 38.7% response rate.

But when a message had no greeting at all -- no salutation or even a simple “hello” – those messages had just a 25.7% response rate.

Providers were also more likely to respond to messages that had a positive sentiment; used expressive punctuation such as question and exclamation marks; and higher word counts. 

To illustrate what they found, researchers asked ChatpGPT to write two messages from the perspective of a patient with respiratory symptoms. 

One message was polite and positive – written in a way to get a high response rate: 

"Dear Dr. Liu, 

I hope you're doing well! I wanted to reach out because I've been experiencing some new respiratory symptoms that I'm a little concerned about and would really appreciate your perspective. Over the past two days, I've developed a dry, persistent cough along with some chest tightness and mild shortness of breath -- especially when walking or going up stairs. 

I haven't had a fever, but the symptoms are definitely noticeable and seem to be getting a bit worse, which is making me wonder if there could be something more going on? I know you've helped me manage my asthma in the past, could this be a flare-up or something else entirely?? 

Thanks so much again for all you do! I really appreciate your time and guidance. 

Warmly, 

Peter Parker

The other patient message was short and blunt – written in a way that researchers thought would get a poor response rate: 

"I've had a cough and congestion for a few days now, and it's been pretty uncomfortable. Still no fever, but it's been dragging on and making it harder to get through the day."

See the difference? The more polite and positive message, though much longer, is more likely to get a response. Writing style was a possible explanation for about half of the disparities that researchers found in response rates. 

“In many message triage systems, nurses and medical assistants must quickly assess messages — often with little context — and make snap judgments on their urgency, complexity, and need for escalation. Given these constraints, it is not surprising that writing style factors might influence the triage process,” researchers said.

Patient portals provide an easy and convenient way for patients to send messages to their physicians, but put an extra burden on doctors to respond. Some do and some don’t – depending on the patient.

So the next time you write a text or message to your doctor, make an effort to be polite and positive. Use words like “please” and “thanks.” Simply being polite can have some surprisingly positive outcomes.  

Is Dry Needling Effective for Muscle Pain?

By The Conversation

Physiotherapists, chiropractors and osteopaths commonly use dry needling to treat neck, shoulder, back and other types of muscle pain.

It involves inserting thin needles into sensitive parts of a person’s muscle, often termed “myofascial trigger points”. The needles remain in the muscle for a few minutes and can be gently moved to create a twitch response in the muscle.

This therapy is thought to relax the muscle, reduce inflammation, promote healing and reduce pain. But does it actually work? And what are the risks?

Similar to Acupuncture

Dry needling is similar to acupuncture: they’re both applied to reduce pain.

Both treatments use solid, single use needles. They’re commonly 30–75mm long and 0.2–0.3mm thick, although longer needles may be used for deeper muscles. Unlike injection needles, they aren’t hollow and don’t inject medication.

A key difference is how the needle locations are chosen. Traditional acupuncture selects points based on symptoms and Chinese medicine concepts, including balancing qi as it flows through pathways called meridians. Dry needling is applied directly to tissue that’s thought to be the cause of symptoms.

Gaining Popularity

People seeing a physiotherapist for aches and pains are increasingly being offered dry needling. A 2023 survey of 203 Australian physiotherapists found 64% use dry needling on their patients.

The surveyed physiotherapists believed dry needling was an effective pain reliever and thought it was particularly effective alongside treatments such as exercise or manual therapy (which encompasses massage and manipulation or “joint cracking”).

In Australia, registered physiotherapists, chiropractors and osteopaths meet the safety standards required to use dry needling if they have completed training. The training usually involves a short (weekend) course.

Does Dry Needling Work?

Several research studies have collated the available evidence on dry needling. Most conclude it provides short-term pain relief for conditions such as neck pain, shoulder pain and low back pain, but is no better than other common treatments such as exercise.

Clinical practice guidelines are what health-care providers should use to dictate which treatments to provide and not provide. However, few clinical practice guidelines recommend dry needling.

There are two main reasons why.

Nearly all studies investigating the benefits of dry needling have serious concerns about how they’re conducted. This includes not being able to determine whether the benefits of dry needling are genuine or simply reflect placebo effects – when your health improves after receiving a fake treatment.

So it remains unclear whether dry needling provides benefits beyond a placebo.

Another reason is the potential risks of dry needling.

What Are the Risks?

Inserting thin and extremely sharp needles into the body requires an excellent understanding of anatomy.

Health-care providers need to be extremely careful to avoid major arteries, veins and nerves when dry needling around the neck and avoid puncturing the lungs when dry needling around the “traps” (trapezius muscles) and torso.

There have been cases of providers puncturing their patients’ lungs during dry needling, prompting a medical emergency.

In June, it was revealed that a Western Australian physiotherapist had her registration suspended for three months after puncturing a patient’s lungs, causing bilateral pneumothoraxes – the collapse of both lungs.

In November, Pittsburgh Steelers NFL player TJ Watts had to undergo emergency surgery after a similar injury caused a partial lung collapse.

Despite the risks, half of the studies on dry needling don’t mention if any adverse events occurred.

The studies that do report risks suggest serious risks such as a collapsed lung, infection or broken needle that gets stuck in a person’s body are very rare.

But we don’t know exactly how rare this is. Data from a large study on acupuncture suggests these adverse events occur in approximately one in 100,000 patients. But it’s unclear if the risk is the same for dry needling.

Less-serious side effects such as minor bleeding, bruising, soreness at the needling site or temporary symptom aggravation seem to be common.

Some factors also increase some risks, such as taking blood thinning medication or having an immune disorder.

Talk to Your Provider

Because the evidence on dry needling is uncertain and risks have not been adequately reported in the research, it’s important to discuss the benefits, risks and practicalities of dry needling with your health-care provider.

If your goal is short-term pain relief, consider asking your provider if there are other options that could provide similar relief.

If you have a fear of needles or have fainted when undergoing a needling procedure previously, such as a blood test, then dry needling might not be the best treatment for you.

Before undergoing dry needling, it’s important you have had a chance to ask questions and been given sufficient information about the treatment before providing informed consent.

Questions you might ask your health-care provider include:

  1. What are my treatment options?

  2. What are the potential benefits and risks of these options?

  3. How likely is it that those benefits and risks could happen to me?

Although other treatments are as effective or more effective with fewer potential side effects, dry needling might be useful for some people. But a discussion of risks and benefits should always be transparent and ongoing.

Luke Jenkins, PhD, is Lecturer in Physiotherapy at Western Sydney University.

Giovanni Ferreira, PhD, is a Research Fellow, Institute of Musculoskeletal Health, at the University of Sydney.

Joshua Zadro, PhD, is an Associate Professor of Physiotherapy at the University of Sydney.

Peter Stubbs, PhD, is an Associate Professor of Physiotherapy at the University of Technology Sydney.

This article originally appeared in The Conversation and is republished with permission.  

Swimming Reduces Disability From Chronic Low Back Pain

By Mark Hancock and Deborah Wareham

As we age, low back pain becomes more common. Between the ages 20 and 59, persistent low back pain (lasting more than three months) affects nearly one in five.

While you may be tempted to reach for heat packs, medication or a massage, new evidence suggests that the common advice to go for a swim is much more effective.

Until recently, there was no research to back up this advice. Our new trial shows for the first time that swimming can improve low back pain.

What We Did

We recruited 76 adults aged 26 to 74 who experienced persistent and bothersome low back pain for more than three months. They needed to be able to swim 25 meters (82 feet) independently, but didn’t swim regularly.

The participants were randomly allocated to receive either a swimming and education program (the intervention group) or education only (the control group).

The intervention involved an eight-week individualised swimming program, supported by four telehealth sessions with a physiotherapist, and free access to a local indoor or outdoor swimming pool.

The amount of swimming was tailored to each participant’s ability and fitness level, with the goal of completing three 30–45 minute swimming sessions per week by the end of the program. Participants were encouraged to continue swimming after the program completed.

The education, provided by a physiotherapist, aimed to help them better understand their pain, reduce the fear associated with movement and exercise, and increase confidence to manage their back pain.

While many people with back pain believe they should avoid activity to protect their back, a large body of evidence shows remaining active is better.

Participants in the education-only (control) group had one to two sessions with a physiotherapist to cover the same key messages about back pain, but otherwise continued their usual treatment and activity.

What Did We Find?

Participants in the swimming group reported improved function, less pain and more confidence to manage future back pain.

Their disability reduced by more than 50% at the end of the eight-week program. This could mean that a person improved their ability to do daily activities such as standing from a chair, walking or sleeping.

The swimming group’s improvements were 30% greater than those who received education only (control) group.

Participants told us swimming appealed to them because it was low-impact, it reduced weight-bearing and strain, and it enabled them to exercise more confidently and with less pain. They also reported additional health benefits, including better mood.

Swimming can be used as a way for people with back pain to start exercising and break the cycle of pain and limited activity.

At the end of the eight-week program, some people kept swimming, others swapped to another form of exercise and some stopped exercising.

Although most participants reported enjoyed swimming, some found accessing a pool and the time required a barrier to keep going in the longer term.

Twelve months after starting the program, there were still benefits for the swimming group for disability, function and confidence. But the difference between groups became smaller over time.

Our study’s sample size was relatively small, so these findings need to be confirmed in future, larger studies.

Further trials are also needed to test whether the results still hold for people with more severe or disabling back pain.

Finally, the volunteers in our study knew we were investigating swimming and had positive expectations of swimming before starting. This is a limitation that could affect the findings.

Swimming vs Other Exercises

A range of different exercises – including Pilates, functional exercises (a type of strength training that helps you perform daily activities) and structured walking – have been shown to be beneficial for treating disability and preventing low back pain recurrences.

While we didn’t compare swimming to another type of exercise, the benefits we identified were as large or larger than previously reported for other exercises.

People with chronic low back pain can now consider swimming as an evidence-based exercise option and be more confident in choosing it as part of their long-term management.

But if you find it a hassle to get to a pool, or don’t like swimming, it may help get your back pain under control before moving to a type of exercise you prefer or can more easily access.

Mark Hancock, PhD, is a Professor of Physiotherapy, Faculty of Medicine and Health Science, at Macquarie University in Australia. 

Deborah Wareham, PhD, is a Research Fellow at the Spinal Pain Research Centre at Macquarie University.

This article originally appeared in The Conversation and is republished with permission.    

Palmitoylethanolamide (PEA): A Natural Treatment for Intractable Pain

By Dr. Forest Tennant and Ingrid Hollis 

Palmitoylethanolamide (PEA) is a naturally occurring biochemical produced by the body for pain and inflammation control. It is also available as an over-the-counter dietary supplement. 

This article is presented with our belief that essentially every person with intractable pain should try a PEA supplement in a therapeutic trial.  Several companies market PEA supplements and researchers have determined effective dosages. 

PEA is the only medicinal that simultaneously fights inflammation at the site of an injury, as well as neuroinflammation in the central nervous system (CNS).  It helps heal damaged glial cells that are responsible for intractable or constant pain. 

About two dozen double-blind clinical studies have shown that PEA is more than just a placebo. German researchers say PEA is an effective and well-tolerated treatment for hundreds of patients with chronic pain.    

Our experience is not as extensive, but we have found that about 80% of patients experience good results if PEA is used for four to six weeks, providing relief for both chronic and intractable pain.  In most patients, PEA progressively wears down baseline pain. 

Starting dosage is 600 to 1200 mg twice a day.  This dosage can be increased if needed.  

Some PEA products contain luteolin, a polyphenol found in many fruits, vegetables and herbs that has anti-oxidant and anti-inflammatory properties. This is excellent as luteolin boosts the effectiveness of PEA, and also helps prevent the reactivation of the Epstein-Barr virus. 

One can simply add PEA to their current pain relief program.  Opioids and other pain medications need not be stopped. 

No serious side effects have been reported from taking PEA. As a natural biochemical, it is quite safe to take.  

If you have chronic or intractable pain, try a 1-to-2-month therapeutic trial of PEA. You have much to gain and nothing to lose. 

Forest Tennant, MD, DrPH, is retired from clinical practice but continues his research on the treatment of intractable pain and arachnoiditis. Readers interested in learning more about his research should visit the Tennant Foundation’s website, Arachnoiditis Hope. You can subscribe to its bulletins here.

Ingrid Hollis is a person in pain, patient advocate, and advisor to the Tennant Foundation.

The Tennant Foundation gives financial support to Pain News Network and sponsors PNN’s Patient Resources section. 

Melatonin Can Help Reduce Chronic Pain

By Pat Anson

Many chronic pain sufferers know how beneficial a good night’s sleep can be. Restorative sleep reduces pain levels, along with fatigue, anxiety and stress.

A new study in Australia suggests that melatonin not only helps with sleep, but is just as effective at reducing chronic musculoskeletal pain as non-steroidal anti-inflammatory drugs (NSAIDs). 

The study, published in the journal PAIN, looked at health data for over 2,000 patients in 23 controlled trials who took melatonin supplements. Participants included people with low back pain, osteoarthritis and fibromyalgia, as well as those recovering from joint replacements and spinal surgeries. 

“For many patients, pain doesn’t exist in isolation and is closely tied to poor sleep,” said lead author and PhD student Kangchao Wu in the Musculoskeletal Research Hub at the University of Sydney. “Melatonin appears to target both, which makes it particularly useful for people managing chronic pain.

Using a zero to 100 pain scale, researchers say melatonin modestly reduced musculoskeletal pain by about nine points, with the most rigorous studies showing pain levels dropping nearly 10 points, a level similar to those of NSAIDs. Melatonin was not as effective in reducing post-operative pain.

Notably, researchers did not find evidence of a dose-response relationship, meaning no single “best” dose of melatonin can be recommended. 

“The level of pain relief we observed is comparable to some conventional treatments, but this does not mean melatonin should replace them,” Wu said. “Rather, it may offer a safer additional option within a broader pain management plan.”

Melatonin is a natural hormone produced by the pineal gland in the brain. During the day the pineal gland is inactive, but at night it begins to produce melatonin and helps us sleep.

Melatonin supplements are widely promoted as sleep aids. However, their role in reducing inflammation – a major contributor to chronic pain – may be just as important. Melatonin has antioxidant and anti-inflammatory properties, which may reduce the central sensitization and inflammation underlying chronic pain.

In Europe and Australia, melatonin requires a prescription, while in the United States melatonin supplements can be purchased over-the-counter.

“Melatonin is already in people’s homes, it’s inexpensive, and we know it’s safe,” says Wu. “What’s exciting is that melatonin may also help manage chronic pain, opening the door to reducing reliance on medications that come with more risks.”

Melatonin is generally well tolerated, with mild, short-term side effects such as nausea, dizziness and headaches. Melatonin is considered safe for short-term use of less than three months. 

A recent study found that adults with insomnia who used melatonin for at least a year were more likely to be diagnosed with heart failure, be hospitalized, or die from any cause. The study did not establish a cause-and-effect relationship, meaning health conditions raising the risk may have already been present. 

Tiny Injectable Implant Could Revolutionize Neuromodulation

By Pat Anson

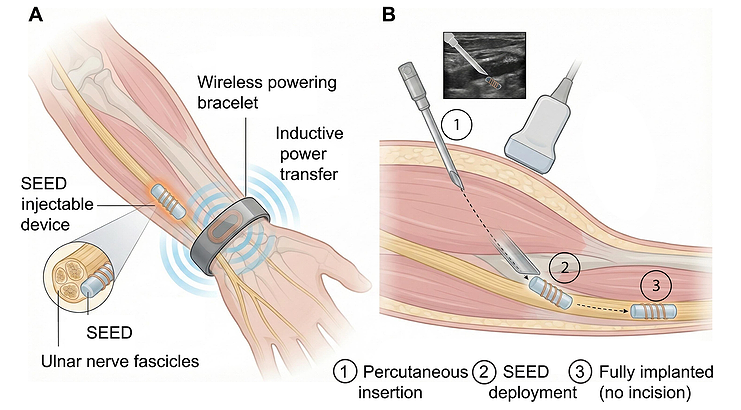
Scientists in Abu Dhabi have developed a tiny neuromodulation device that can treat chronic nerve pain without the need for invasive surgery. 

The experimental device is so small – about the size of a small seed – that it can be injected into the body with a standard needle. It is powered wirelessly from outside the body, allowing doctors or patients to adjust its neuromodulation levels in real time.

“This work represents a shift in how we think about treating nerve-related conditions,” said Khalil Ramadi, PhD, an Assistant Professor of Bioengineering at NYU Abu Dhabi and senior author of a research paper published in Science Advances. 

“By creating a device that can be injected rather than surgically implanted, we are making these therapies simpler, safer, and more accessible, while still maintaining precise control over nerve activity.”

Current neuromodulation methods, such as spinal cord stimulation and transcutaneous electrical nerve stimulation (TENS), have their limits. 

TENS units are not invasive and easy to operate, but can cause uncomfortable tingling sensations for patients. They also stimulate a wide area, activating nerves and muscles that don’t need treatment. 

Spinal cord stimulators require invasive surgeries near the spine, and come with implanted wires and batteries that can malfunction, need replacement, and cause infections.

Because the SEED (Stimulating Electrode for Electroceutical Delivery) implant is injected, it can be placed and tracked with standard medical imaging, such as ultrasound and CT scans, allowing it to target a specific nerve. 

Once implanted, it delivers mild electric signals that can be programmed and tailored for each individual patient. Power for the device is delivered wirelessly from an external battery that can be worn on the wrist.

SCIENCE ADVANCES

The SEED device is in the preclinical stage and has only been tested on the peripheral nerves of laboratory rats. Researchers say the device demonstrated precise control over nerve stimulation and performed consistently.

“This technology has the potential to bridge the gap between non-invasive therapies and traditional implants,” said first author Mohamed Elsherif, PhD, Research Associate at NYU Abu Dhabi. “It opens the door to treatments that are both effective and easy to deliver, which could significantly improve patient care.”

The SEED implant will likely need to be tested on larger animals, such as pigs or sheep, before human trials can begin. Clinical use of the device will require FDA approval and is at least 5 to 10 years away. 

Researchers at Rice University are developing a similar device – about the size of a grain of rice – to treat neuropathic pain. Like the SEED implant, the device has not been fully tested on humans.   

I Hate When Doctors Insist on Physical Therapy for Chronic Pain

By Crystal Lindell

There is definitely an over-prescription crisis in this country, but it’s not about pills – it’s physical therapy referrals. 

While many doctors see it as an “easy” way to reduce their opioid prescribing, the only thing easy about it is how easy it is for them to write the referral and then immediately blame the patient for any lack of progress. 

In fact, I recently stumbled onto a discussion about physical therapy in the “Family Medicine” subreddit, where medical professionals, who’ve confirmed their credentials, were discussing just how much they love to push PT on patients and why. 

In the thread, a poster who claims to be a new physical therapist asked providers when they typically will prescribe it. 

A nurse practitioner responded with, "I only prescribe PT on days that end with Y." 

A physician's assistant said they prescribe physical therapy "as soon as [patients] open the door."

A medical doctor lamented, "I wish my patients took [physical therapy] more seriously because recovery for a lot of [musculoskeletal] and chronic pain takes work and they want the one shot fix."

Ironically, it really seems that it’s the doctors who are looking for a one-shot fix with their physical therapy referrals. As another doctor on the thread admits, they prescribe PT "for any pain, gait, chronic respiratory, chronic pulmonary, or weakness complaints."

As a long-time pain patient, the thread confirmed everything I assumed doctors thought about pain patients and physical therapy. But unless you’re recovering from a specific injury, like a bone break or surgery, physical therapy can be a huge waste of time and money. 

For patients, the reality is that physical therapy is a massive time commitment and a huge financial expense.

Way back before I even developed intercostal neuralgia in my ribs, I started having pain in my wrists, likely caused by years of undiagnosed Ehlers Danlos syndrome and typing for a living. The official diagnosis for me at the time was “tendonitis.”

As someone who writes for work, dealing with sudden wrist pain was causing me massive issues. There were days when the pain was so intense that I couldn’t even type up a column.

I was also younger and more naïve then, so at the time my only goal was to do everything my doctor told me to do. I genuinely believed that that was my best chance at getting better, and that he had my best interest at heart. 

So when he told me to take Advil and go to physical therapy three times a week, I happily agreed.

The only issue was that I had to miss a ton of work, use a bunch of gas to get to the appointments, pay for parking, and then also come up with the $30-per-session co-pay, which added up to almost $100 a week! Times that by four weeks, and suddenly you’re looking at a car payment, easy.

God forbid, you have a job where you can’t get time off during the limited business hours offered by physical therapists. Plus, there’s the issue of finding a babysitter if you have kids.

Maybe that’s not a lot of money to doctors, but to many patients it’s enough to put you into crushing debt and maybe even lead to you losing your job for missing too much work.

The worst part was that physical therapy did almost nothing to relieve my pain. The appointments themselves mostly consisted of the therapist massaging my wrists, which only helped in the moment. In truth, the most effective part was the wrist braces they gave me to sleep in, something my primary care doctor could have easily given me himself.

Many doctors seem to think that if a patient is “really” in pain, they will try anything to get better. And thus, if a patient is reluctant to spend a bunch of time and money on physical therapy, then the only logical conclusion is that they must be a drug-seeking junkie looking to get high.

But there’s a reason that pain medication, especially opioids, are so popular. They are known to be immediately effective, and they are very cheap compared to physical therapy. Plus, instead of forcing you to miss work, they actually allow you to go to work despite the pain.

Looking back, I do not think that I needed opioid medication for my wrist pain, so I’m not arguing for that. I’m just saying that I also did not need physical therapy. But, like many of the doctors on that Reddit thread, my physician had gotten into the habit of prescribing PT for almost anything. 

Unfortunately, that would not be the last time a doctor tried to push physical therapy onto me. It happened to me and my loved ones many times over the years. While I have seen it work for family members who had just had a major operation or an acute injury, I have rarely seen it help much with chronic pain.

Of course, there are certainly patients who have benefited from it, and physical therapy should definitely be an “easy” option for them. Unfortunately, insurance coverage of PT is often limited. My fiancé can’t get insurance to cover any more physical therapy for him, despite the fact that he does find the sessions to be beneficial for his chronic pain.

In essence, doctors will happily prescribe physical therapy, but that’s about where their concern ends. After that, you need to figure out the health insurance requirements, assuming you even have insurance. Then you have to come up with co-pays, transportation, time off work, potential babysitters, and the energy to go to PT appointments while also maintaining the rest of your responsibilities. 

That last one is something doctors often fail to consider. If you’re working one or more jobs, running a household, and trying to get through the week, adding in the time and emotional energy to go to physical therapy a few times a week can be almost impossible.

In short, there’s a long list of negative side effects that come with physical therapy. They start with the referral by your doctor. Physical therapy should not be used by them as a secret test that patients have to pass just to prove they’re not trying to score some hydrocodone. It also shouldn’t be used as a first-line treatment for patients who may greatly benefit from other treatments.

There were a couple people on that Reddit thread attempting to stick up for patients. One doctor said this: 

"To be fair, it's financially out of reach for many (most of my) patients. My low income patients can get 4 visits/year but finding a PT who can provide the low income service can be challenging. These same patients are getting a maximum income support of $1787/month (a 700 square foot basement apartment rents for about $1500/mo right now in our city, if you can find one).

Sometimes people don't make bad choices, they fail to have good choices to make."

The only problem with that response is that it still assumes that physical therapy is a “good” choice. As a patient, I’m not convinced that it is. In fact, sometimes it’s a bad one. 

Glucosamine May Contribute to Alzheimer’s Disease

By Pat Anson

An over-the-counter supplement used by millions of people around the world to relieve joint pain has been associated with Alzheimer’s disease and other advanced forms of dementia, according to a new study.

Neuroscientists at the University of Florida say glucosamine raises the risk of someone progressing from mild cognitive impairment to Alzheimer’s disease by about 25 percent.

Glucosamine is an amino sugar found in shellfish that helps build cartilage, ligaments, tendons, and synovial fluid in joints. It is used annually by about 40 million Americans, many of them elderly, to reduce inflammation and symptoms of osteoarthritis.

What many seniors don’t realize is that glucosamine may also be accelerating the formation of protein plaques in their brain, which have been linked to dementia. 

“A lot of these people actively take an over-the-counter supplement that could be making their disease progression worse,” senior author Ramon Sun, PhD, a biochemist and molecular biologist, said in a press release.

It’s important to note that the study findings, published in the journal Nature Metabolism, are preliminary and don’t establish a cause and effect relationship between glucosamine and Alzheimer’s – only an association.

The findings are based on a large retrospective analysis of health records for over 50,000 patients diagnosed with Alzheimer’s disease-related dementias (ADRDs) or mild cognitive impairment (MCI). While most patients with MCI remained stable or even recovered cognitive ability, about 5% progressed to ADRD, representing a clinical worsening of cognitive decline. 

About 8% of the patients studied reported taking glucosamine supplements. When compared to patients who didn’t take glucosamine, researchers saw a 25% higher risk of patients with MCI transitioning to ADRD in the glucosamine user group. In addition, glucosamine use was associated with a 25% increase in mortality risk among ADRD patients.

Researchers believe glucosamine crosses the blood-brain barrier and feeds into pathways that build sugar residue on protein cells. Patients with Alzheimer’s appear to be more vulnerable to this metabolic activity than those with healthy brains.

“The electronic health record data are very provocative,” said co-author Matt Gentry, PhD, chair of UF’s Department of Biochemistry and Molecular Biology. “While it’s an association and not proof of causality, it does raise an important clinical question that now deserves much more attention.”

In tests on genetically modified mice, the UF research team found that glucosamine significantly increased sugar residue on proteins in the brain and reduced the social recognition behavior of mice. When researchers chemically suppressed this process, their “social memory” improved.

Advanced imaging studies on human Alzheimer’s brains also showed significantly increased sugar attachment to proteins compared to healthy brains. 

Taken together, the findings suggest that metabolic dysfunction is not simply a secondary aspect of Alzheimer’s pathology, but a contributing cause. 

“Proteins are the cell’s molecular machines, and many of them need sugar tags added in just the right way to fold correctly, travel to the right place and do their jobs,” Gentry said. “What we found in Alzheimer’s is that this sugar-tagging system appears to be overactive. The Alzheimer’s brain is adding too many of these sugar structures, and this seems to contribute to the disease rather than protect against it.”

The good news about this research is that it could lead to new ways to prevent Alzheimer’s or slow its development.

“Our results suggest that altered metabolism is a significant contributor to Alzheimer’s progression and, in addition, addressing the metabolic defect could be an important complement to approaches focused on Alzheimer’s plaques and tangles,” Sun said.    

Glucosamine is the fourth most widely used supplement in the United States. It is also widely used in China and Europe. Glucosamine is often combined with chondroitin to help build or restore joint cartilage. 

While further studies are needed, the Mayo Clinic says glucosamine “might provide some pain relief” for people with knee osteoarthritis.
